A woman in her late forties notices in a photograph that her head is turned a little to the right, the way it has been in every photograph for a year. She has had a right-sided neck ache for longer than that. Massage helps for a day. A cervical MRI showed “age-appropriate changes.” She has never told anyone that resting two fingers against her chin makes the neck feel normal for a minute, because it sounded strange. Those four details — the turned head, the one-sided ache, the normal scan, and the touch that helps — are the early symptoms of cervical dystonia, and together they are close to diagnostic.
The early signs, in the order patients notice them
The first symptom is usually the drift. Late in the day, walking, or under stress, the head turns or tilts a few degrees to one side, and it comes back when the patient notices and corrects it. At this stage most people call it posture. The second is the ache: one-sided, in the muscles between the ear and the collarbone or at the back of the neck on the same side, soothed by heat, massage, or a muscle relaxant for a day at a time and never gone. The third is a shoulder that sits higher on the pulling side, noticed in a mirror or by a partner. The fourth is difficulty holding the head still for tasks — reading, driving, a screen — that takes effort the patient cannot explain. Somewhere in the first year most patients discover the sensory trick on their own, and most do not mention it.
Onset is typically between 40 and 60, women more often than men, and the symptoms build over weeks to months rather than appearing overnight. A head that has not stayed where you put it for two to three weeks is a sensible point to stop calling it a stiff neck and get it examined.
The full picture: posture, trick, tremor, pain
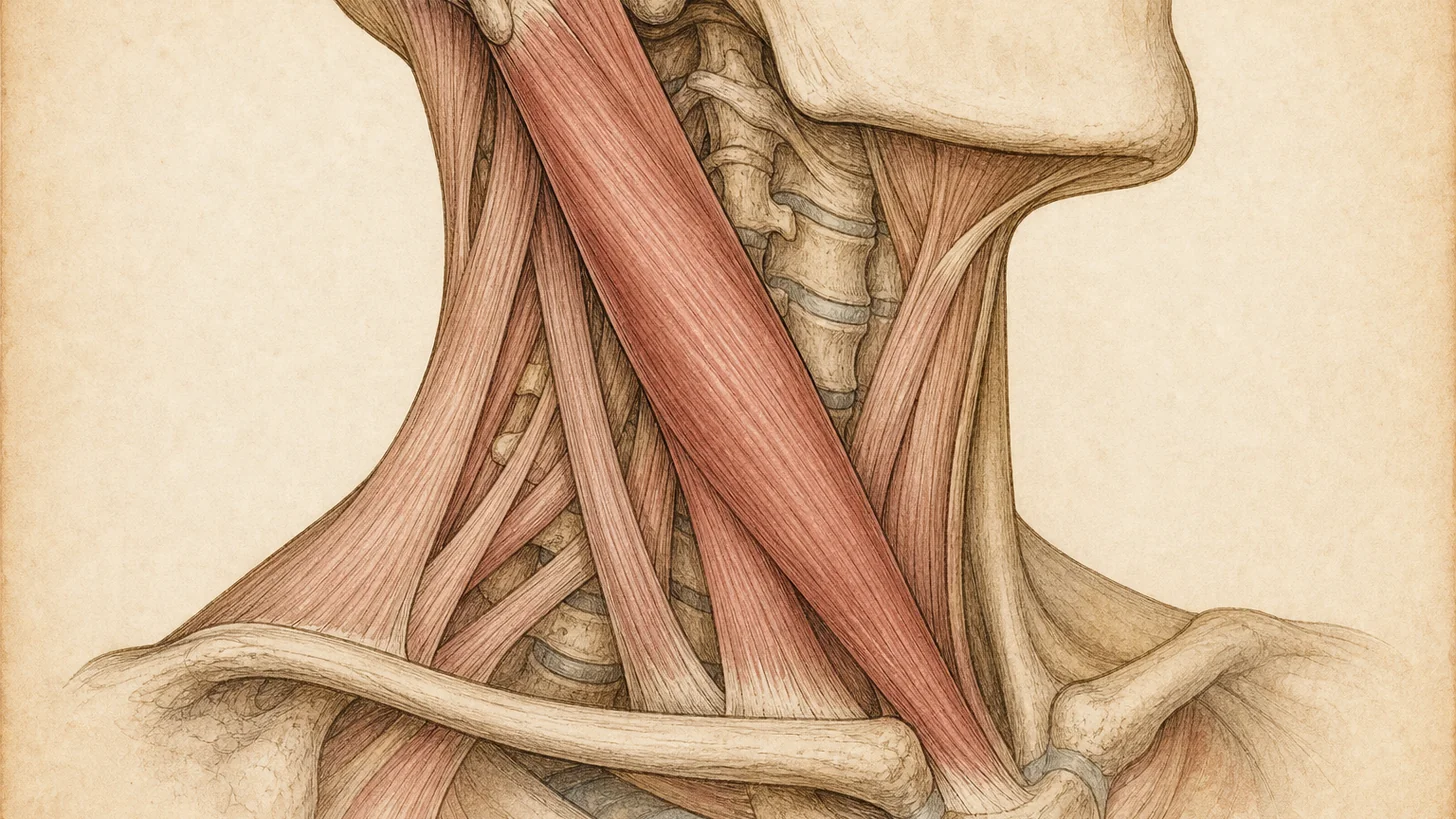
The four head positions. Rotation of the chin toward one shoulder is torticollis, the most common pattern. A tilt of the ear toward the shoulder is laterocollis. A pull of the chin toward the chest is anterocollis, and a pull backward is retrocollis. A sideways or forward shift of the whole head adds two more, and most patients have a combination — a turn with a tilt, say — because several muscles are involved. The direction matters because it names the muscles that are firing, which is what the injections are mapped to (Albanese 2013).
The sensory trick (geste antagoniste). A light touch to the chin, cheek, jaw, or back of the head reduces the pull far more than the mechanical force of the touch could explain. Some patients get the same effect from a scarf, a collar, or leaning the head against a headrest. Most patients have one, few volunteer it, and it is rare in other causes of neck pain, which makes it one of the most useful questions in the history.
The tremor. Many patients have a head tremor, and it is a specific kind: jerky, irregular, direction-specific, and worse when the patient tries to hold the head straight against the pull. It settles when the head is allowed to sit in its preferred position. That pattern separates dystonic tremor from essential tremor, which is smooth, rhythmic, and present in any position, and it is the reason patients with early cervical dystonia are sometimes told they simply have “a tremor.”
The pain. In the CD PROBE registry of 1,037 patients, pain was frequent enough that the investigators called it important in choosing a treatment, and the patients with moderate or severe pain had higher severity and disability scores and were treated with higher doses into more muscles (Charles 2014). It sits in the muscles doing the pulling — sternocleidomastoid, splenius, levator scapulae, upper trapezius — on the side the head pulls toward, and it improves when those muscles are quieted, which is the reverse of most degenerative neck pain. Headache starting at the base of the skull on the pulling side is common. After years of one-sided pull, the cervical spine on that side develops facet arthritis and disc changes, and a second, mechanical pain layers on top of the dystonic one.
Visible muscle change. The sternocleidomastoid or the splenius on the working side is often thicker, and the examiner can feel it. Shoulder elevation on that side is part of the same picture.
Course over the day. Worse when tired, stressed, anxious, or walking. Better lying down, in the morning, and with the trick. Alcohol briefly improves it in some patients.
Beyond the neck. In a minority the dystonia spreads to the jaw, the eyelids, or a hand, or begins there. Spread, onset before 30, or any other neurological sign changes the workup and brings neurology in from the start. Anxiety and low mood are common, are partly part of the disorder rather than only a reaction to it, and are worth naming at the visit.
What it is not
Three conditions cause an abnormal neck position or a one-sided neck pain and are routinely confused with cervical dystonia. Acute torticollis is a muscular spasm with a trigger — an awkward night, a sudden movement, a viral illness — that resolves within days to a week with rest and anti-inflammatories, and there is no involuntary command pulling the head over time. Cervical strain, including whiplash, is a soft-tissue injury with pain that is reproduced by movement and pressure and usually improves over weeks, with no involuntary head movement. Cervical myofascial or facet-driven neck pain produces one-sided ache and spasm, but the head stays straight and moves normally, nothing eases it except rest, and it is treated with trigger point injections or a medial branch block rather than botulinum toxin.
The practical rule: an abnormal head position that has lasted more than two to three weeks, returns reliably, or feels pulled against your will should be evaluated for cervical dystonia. The word torticollis is used for both the acute spasm and the chronic dystonia, which is part of why the diagnosis takes so long.
Two other things are excluded on the first visit. Dopamine-blocking drugs — metoclopramide, prochlorperazine, most antipsychotics — can produce an identical picture called tardive dystonia, and the medication list is reviewed. Anyone under 40 is screened for Wilson disease with a serum ceruloplasmin.
Why it gets missed for years
In a survey of 108 patients at a U.S. academic center, people saw an average of 3.5 providers over about 44 months before anyone named the condition, though patients whose symptoms began in the most recent decade were diagnosed faster, in about 14 months (Tiderington 2013). The reasons are consistent. The early posture is subtle and gets called posture. The pain is real and gets treated as a strain, which briefly works. The scan shows the degeneration that is common after forty, and the report becomes the diagnosis. Nobody asks about the trick, and nobody watches the patient walk. The cost of the delay is years of pain, secondary spine damage, and the anxiety of a symptom without a name.
How the diagnosis is confirmed
The diagnosis is clinical. There is no blood test or scan that confirms cervical dystonia. The examiner watches the head at rest, in conversation, while walking, and while the patient tries to hold it straight, then asks the patient to use their trick and watches what changes. The neck muscles are palpated for tone and hypertrophy, range of motion is measured against the pull and with it, and the tremor is characterized. Severity, disability, and pain are scored on the Toronto Western Spasmodic Torticollis Rating Scale, which is the scale used in every trial and the one used to measure response cycle over cycle. Imaging is ordered to rule things out rather than in: a cervical MRI when there are arm symptoms suggesting a pinched nerve in the neck, a brain MRI when onset is young or the dystonia is spreading. The full examination and the treatment ladder are on the cervical dystonia treatment page.
Read the film's transcript
Your head won't stay where you put it. It turns or tilts on its own, and a touch on your chin somehow helps.
That isn't a stiff neck, and it isn't stress. It's cervical dystonia, and these neck muscles are only doing what they're told.
The fault is the order. The brain network that shapes movement has lost its brake, so the signal never fully switches off. A touch feeds it new information, and the pull eases.
Every order ends in a handshake between nerve and muscle. Packets of messenger cross the gap, and the fiber tightens. Botulinum toxin, whether it's Botox, Dysport, or Daxxify, slips into that ending and cuts the docking protein, SNAP-25. The packets stay locked, and the muscle goes quiet.
So the injections go only into the muscles that pull, guided by EMG and ultrasound, while the other side keeps working. The goal is less pull, less pain, a head closer to the middle.
Usually, it's a sore or weak neck, some tiredness, or trouble swallowing for a few weeks. Rarely, weakness that spreads, or trouble breathing. These need the nearest emergency room, or call 911.
It's approved for cervical dystonia, it's the first-line treatment, and it's repeated in cycles, with therapy in between. Educational only. See a specialist.
What treatment does to the symptoms
Botulinum toxin injected into the specific muscles that are pulling is the first-line treatment. In the Cochrane review of nine randomized trials, a single session produced a clinically relevant reduction in severity, disability, and pain at four weeks, with no efficacy difference between the approved type-A products (Rodrigues 2020). Pain often improves early. The tremor typically settles with the pull. The effect lasts about twelve weeks with Botox™ or Dysport™ and longer with Daxxify™, and the muscle map is re-examined at every cycle because the pattern shifts. At Modal Pain Management NYC, Dr. Movshis performs the injections under EMG guidance, which shows the needle is in a muscle that is actively firing, and adds ultrasound to reach the deep muscles safely. Pattern-specific physical therapy between cycles helps: in a randomized trial of 40 patients, adding a structured physical therapy program to botulinum toxin gave a longer benefit, a lower dose at reinjection and less pain than toxin alone (Tassorelli 2006). What the injection visit involves, how many units, and what it costs are in Botox for cervical dystonia: what to expect. Spontaneous remission happens in roughly one patient in ten and is usually temporary, so the plan is control, on a twelve-week rhythm, rather than waiting.
If your head does not stay where you put it, and a touch to the chin brings it back, that is the visit to book.
References
This article is reviewed against the peer-reviewed literature. Citations retrieved from PubMed.
- Albanese A, Bhatia K, Bressman SB, et al. Phenomenology and classification of dystonia: a consensus update. Movement Disorders. 2013. doi:10.1002/mds.25475 · PubMed
- Tiderington E, Goodman EM, Rosen AR, et al. How long does it take to diagnose cervical dystonia? Journal of the Neurological Sciences. 2013. doi:10.1016/j.jns.2013.08.028 · PubMed
- Charles PD, Adler CH, Stacy M, et al. Cervical dystonia and pain: characteristics and treatment patterns from CD PROBE (Cervical Dystonia Patient Registry for Observation of OnabotulinumtoxinA Efficacy). Journal of Neurology. 2014. doi:10.1007/s00415-014-7343-6 · PubMed
- Rodrigues FB, Duarte GS, Marques RE, et al. Botulinum toxin type A therapy for cervical dystonia. Cochrane Database of Systematic Reviews. 2020. doi:10.1002/14651858.CD003633.pub4 · PubMed
- Simpson DM, Hallett M, Ashman EJ, et al. Practice guideline update summary: Botulinum neurotoxin for the treatment of blepharospasm, cervical dystonia, adult spasticity, and headache [RETIRED]: Report of the Guideline Development Subcommittee of the American Academy of Neurology. Neurology. 2016. doi:10.1212/WNL.0000000000002560 · PubMed
- Tassorelli C, Mancini F, Balloni L, et al. Botulinum toxin and neuromotor rehabilitation: An integrated approach to idiopathic cervical dystonia. Movement Disorders. 2006. doi:10.1002/mds.21145 · PubMed
Frequently Asked Questions
Four things, in most patients in some combination. An involuntary head posture, with the chin turning toward one shoulder, the ear tilting toward a shoulder, or the head pulling forward or back. A sensory trick, where a light touch to the chin, cheek or back of the head eases the pull far more than the force of the touch could explain. A jerky, irregular head tremor that worsens when you try to hold the head straight. And pain in the muscles doing the pulling. In the CD PROBE registry, patients with moderate or severe pain had higher severity and disability scores (Charles 2014). The muscles on one side are often visibly thicker.
The earliest sign is usually a head that drifts to one side when you are tired, walking, or stressed, and comes back when you concentrate on it. Alongside that, a one-sided neck ache that muscle relaxants and massage soothe for a day at a time, a shoulder that sits higher on one side, and difficulty holding the head still to read or drive. Many patients have already discovered the sensory trick and never mentioned it because it seemed odd. Symptoms develop gradually over weeks to months, most often between 40 and 60, and a head that will not stay where you put it for more than two or three weeks is the sign to act on.
Patients describe a pull rather than a stiffness: the head is being turned or tilted by something they did not ask for, and holding it straight takes effort that tires quickly. The neck muscles on the pulling side ache, burn, or cramp, and the ache is worst late in the day and after walking. Lying down eases it, so mornings are often the best part of the day. The tremor, when present, is felt as the head shaking or nodding when trying to keep it centered. Anxiety and low mood are common alongside the physical symptoms and are partly part of the disorder, not only a reaction to it.
No. A stiff neck or acute torticollis is a muscular problem with a trigger — an awkward night, a sudden movement, a viral illness — that resolves within days to a week with rest and anti-inflammatories, and the head is not being pulled by an involuntary command. Cervical dystonia is a neurological movement disorder in which the brain sends a sustained contraction command to specific neck muscles, the posture persists for years without treatment, and the sensory trick and the direction-specific tremor are present. The word torticollis is used for both, which is part of why cervical dystonia is misdiagnosed for so long.
Rarely, and usually not for good. Spontaneous remission is reported in roughly one patient in ten, mostly in the first few years, and most of those remissions are temporary. The condition does not shorten life, but untreated it is chronic, and the years of one-sided pull produce secondary problems in the cervical spine. Botulinum toxin injections into the specific overactive muscles are the first-line treatment, with a clinically relevant reduction in severity and pain from a single session in the Cochrane review of nine trials (Rodrigues 2020), and control rather than cure is the realistic goal.
Stress, fatigue, walking, anxiety, and prolonged desk or screen work make the pull worse in most patients, and lying down, sleep, and the sensory trick make it better. Alcohol briefly improves it in some. A flare that appears three months after the last injection is usually the treatment wearing off rather than a trigger, and it is the signal to schedule the next cycle. New or worsening symptoms after starting a dopamine-blocking medication — metoclopramide, prochlorperazine, most antipsychotics — need a medication review, because those drugs can produce an identical picture.
When the head pulls, tilts, or turns on its own for more than two to three weeks, returns reliably, or interferes with driving, sleep, or work — and sooner if a touch to the chin eases it, which is a strong clue. In a survey of 108 patients at a U.S. academic center, people saw an average of 3.5 providers over about 44 months before the diagnosis was made (Tiderington 2013). A movement-disorder neurologist or an interventional pain physician trained in EMG and ultrasound-guided botulinum toxin can confirm the diagnosis by exam at the first visit. Onset under 30, dystonia spreading to other body regions, or other neurological signs are reasons to involve neurology from the start.