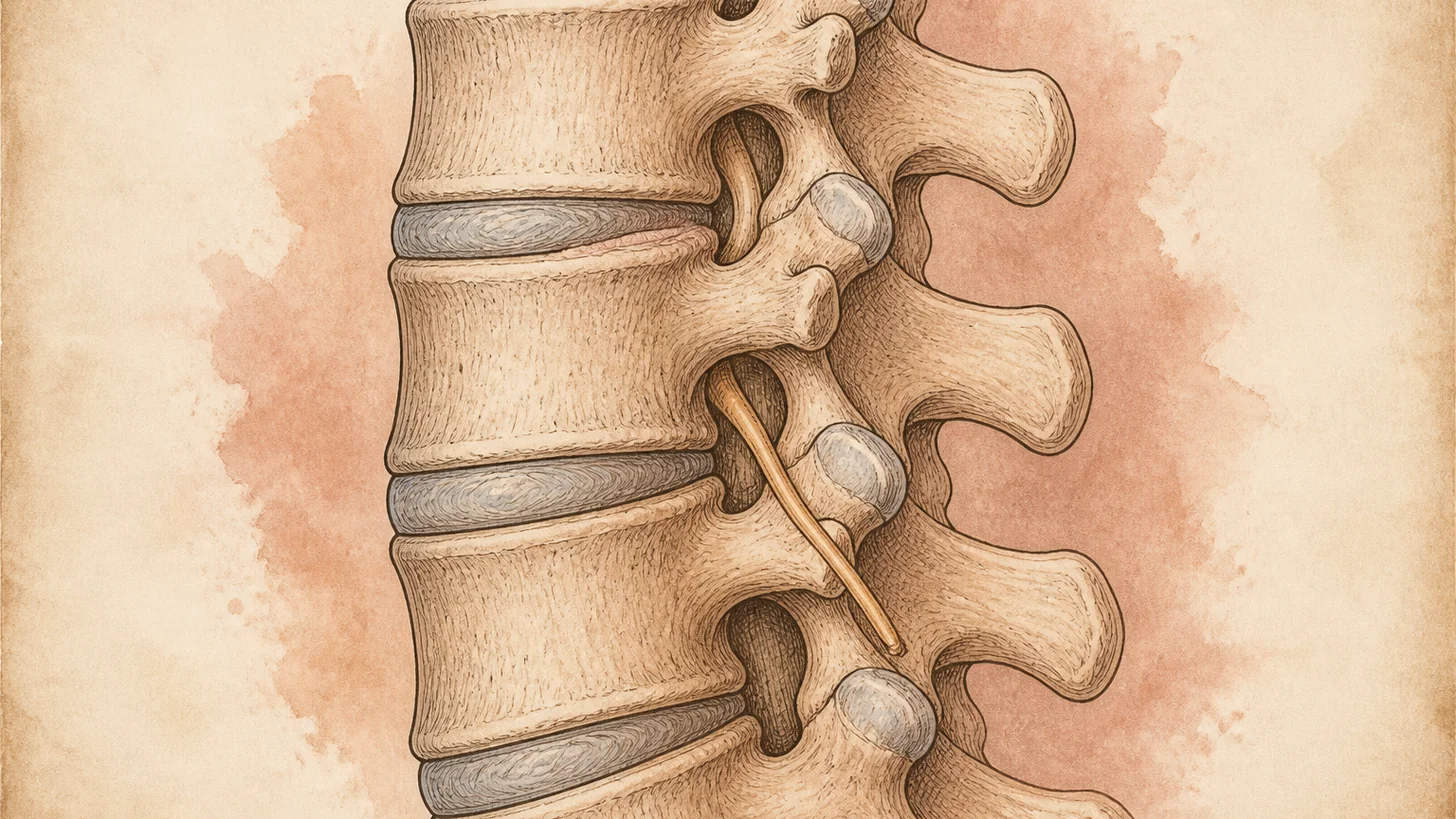
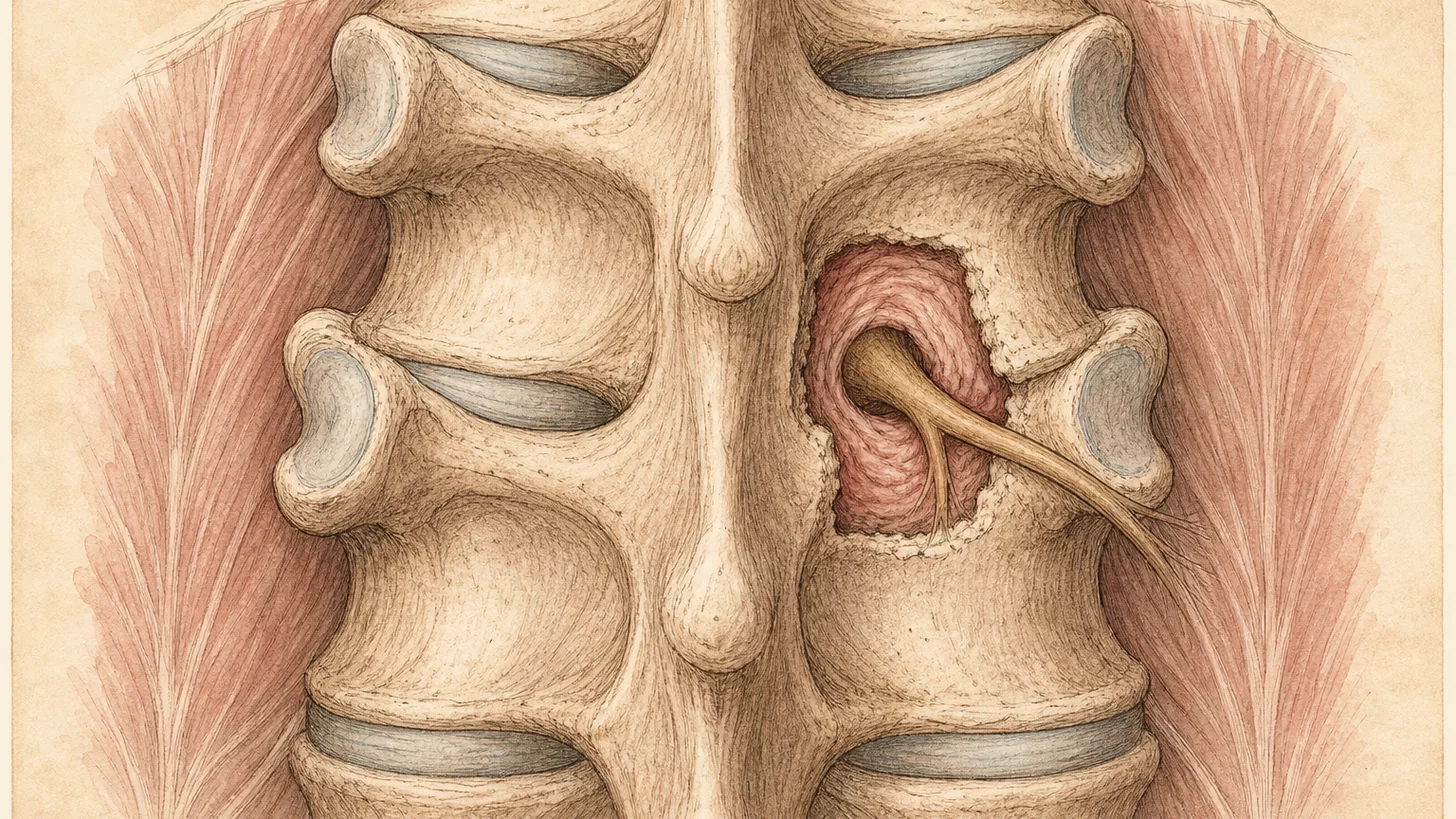
A 41-year-old who commutes into Midtown on Metro-North has had right-sided low back pain for five months, worse after the train ride and worse climbing out of a cab. Asked where it hurts, she points with one finger to a spot just below the belt line, beside the bony bump at the back of the pelvis. She has had two courses of physical therapy for a “lumbar strain” and an MRI reporting a disc bulge at L4–5, a finding common in people her age with no pain at all. Nobody has pressed on the spot she points to or run the sacroiliac joint tests. The bulge was never the problem.
Chronic back pain comes from a short list of structures, each with its own exam finding and its own procedure. Dr. Alex Movshis examines for all of them at the first visit at Modal Pain Management. He trained in anesthesiology at The Mount Sinai Hospital and in interventional pain medicine at the Icahn School of Medicine at Mount Sinai, and he is board-certified by the American Board of Anesthesiology in Anesthesiology and in Pain Medicine.
What a back pain specialist checks, and what each finding points to
The exam usually narrows the field within minutes. This is the map Dr. Movshis works from, and the first-visit section below describes the exam itself.
| What the exam finds | Points to | Confirmed by |
|---|---|---|
| Ache beside the spine, worse arching back, eased leaning forward, nothing below the knee | Lumbar facet joint | Medial branch blocks |
| One-sided pain below the belt line, one finger on the back of the pelvis, three or more positive SI tests | Sacroiliac joint | Image-guided SI joint injection |
| Leg pain worse than back pain, below the knee, positive straight-leg raise, a weak toe or ankle | Herniated disc on a nerve root | MRI at the predicted level |
| Midline ache worse sitting and bending, normal leg exam | Painful disc, no pinched nerve | Exam and MRI together |
| Legs heavy standing and walking, better sitting or leaning forward | Lumbar spinal stenosis | MRI plus the history |
| One tender point on the iliac crest, about 7 cm from the midline, that reproduces the pain | Cluneal nerve entrapment | Ultrasound-guided cluneal nerve block |
| Deep buttock pain on sitting, normal back exam | Piriformis, ischial bursa, or hamstring tendon | Exam and ultrasound-guided injection |
| Taut bands beside the spine or in the quadratus lumborum that reproduce the pain | Myofascial pain | Response to trigger point injection |
| Ache between or below the shoulder blades, tender over one segment | Thoracic facet or rib joint | Thoracic medial branch block |
| Burning band along one rib, skin tender to touch | Intercostal neuralgia | Intercostal nerve block, after heart and lungs are cleared |
Two cautions keep the table honest. The exam narrows and the block confirms. A major review of lumbar facet pain found that no history or exam finding diagnoses it alone, and that even a low-volume anesthetic block has a high false-positive rate (Cohen 2007), which is why a joint is confirmed before it is ablated. And most back pain never gets a precise source because it does not need one. Most new episodes recover quickly (Hartvigsen 2018), with average pain in pooled acute cohorts falling from 52 to 23 out of 100 within six weeks (da C Menezes Costa 2012). This sorting is for the pain that did not. Among patients with resistant pain who were tested until a source was found, the disc accounted for 42%, the facet joints 31%, and the SI joint 18% (DePalma 2011).
Lower back pain: the named diagnoses and their procedures
Facet joint pain. The ache sits beside the spine rather than on it, builds with standing and leaning back, eases sitting or bent forward, and rarely passes the knee. MRI cannot pick the painful joint, so medial branch blocks make the diagnosis and radiofrequency ablation of the same nerves treats it. In a prospective audit of 15 patients selected by controlled blocks, 60% had at least 90% relief at twelve months (Dreyfuss 2000). The international consensus guideline names the trade-off: stricter block criteria improve ablation results but miss some patients who would have responded (Cohen 2020). Why arching backward hurts covers the mechanics.
Sacroiliac joint pain. One-sided pain below the belt line, often pointed to with a single finger just inside the bony bump at the back of the pelvis, sometimes spreading to the buttock, thigh, or groin. Dr. Movshis runs the SI provocation battery on everyone with low back or buttock pain. Three or more positive tests out of six identified injection-confirmed SI joint pain with 94% sensitivity and 78% specificity, and when none reproduced the pain the joint could be ruled out (Laslett 2005). The SI joint was the source in 30% of patients with pain centered below L5–S1 in a single-block study (Schwarzer 1995) and in 12 of 28 patients with persistent pain after a lumbar fusion (DePalma 2011, fusion series). An image-guided SI joint injection confirms and treats, and SI joint radiofrequency ablation follows when the relief keeps wearing off. The SI joint pain page has the full workup.
Herniated disc and sciatica. When the leg hurts more than the back, the question is a nerve root. The pain follows the root’s strip, L5 across the top of the foot to the big toe, S1 to the outer foot and sole. Sitting and coughing set it off, the straight-leg raise reproduces it, and a weak big-toe lift or a missing ankle reflex names the level. The herniated disc and sciatica pages go deeper, and the herniated disc animation and the sciatica animation each show the mechanism in just over a minute. For a root that stays inflamed, a transforaminal epidural steroid injection goes to the level the exam and the MRI agree on. The pooled trials show a small immediate reduction in pain and a lower short-term chance of surgery, below the threshold for a clinically important difference and without long-term advantage (Chou 2015).
A painful disc without a pinched nerve. Midline pain that builds with sitting and bending and eases with walking, with a normal leg exam. The dark, dehydrated disc on the MRI is also common in pain-free spines (Brinjikji 2015). No single procedure fixes it reliably, so the plan centers on graded loading. The disc degeneration animation shows why a frightening scan is not always the pain.
Spinal stenosis. Legs that turn heavy or numb standing and walking and recover within minutes of sitting or leaning on a shopping cart. The most useful single findings are no pain when seated (likelihood ratio 7.4), relief bending forward (6.4), and pain in both buttocks or legs (6.3) (Suri 2010). Treatment starts with a flexion-based walking program. The pooled trials found no clear benefit from epidural steroids in stenosis (Chou 2015), so an injection is a tool for a flare, not the plan. The spinal stenosis page has the workup, and the stenosis animation shows why leaning forward helps.
Cluneal nerve entrapment. Small sensory nerves cross the back of the iliac crest through a tight tunnel about 7 cm from the midline and can be pinched there. The pain passes for ordinary low back and buttock pain, sometimes with leg symptoms, and survives negative facet and SI workups because neither test touches these nerves. The anchor finding is one tender point on the crest that reproduces the whole complaint. Of 834 patients with low back or leg symptoms in a prospective study, 113 (14%) met the criteria, and 68% of those had their pain cut by more than half after up to three blocks (Kuniya 2014). An ultrasound-guided block confirms and treats it, as the guide to cluneal nerve entrapment explains.
Deep buttock pain when sitting. Pain deep in one buttock that builds on a chair, with a normal back exam, usually comes from the piriformis muscle, the bursa over the sitting bone, or the hamstring tendon. Buttock pain when sitting sorts them, and piriformis syndrome covers the ultrasound-guided injection for the muscle.
Muscle. Taut bands beside the spine and in the quadratus lumborum reproduce the pain when pressed. Sometimes that is the whole story. More often it is a layer over one of the sources above, since muscle guards a painful joint. Trigger point injections break the cycle so the exercise program can work, and muscle spasms and myofascial pain covers the rest.
Mid-back pain: the thoracic routes
Thoracic pain gets less attention than neck or low back pain and is common in desk work. Across occupational groups, one-year prevalence ranged from 3% to 55%, with most near 30% (Briggs 2009). Every thoracic vertebra carries a pair of ribs, so each level adds rib joints and a nerve that wraps around the chest.
Muscle, posture, and the neck. The commonest version is an ache between the shoulder blades that builds through the workday, from the rhomboids and middle trapezius loaded for hours. The one most often missed comes from the neck. In discography mapping, the discs from C3–4 to C7–T1 each referred pain between the shoulder blades (Slipman 2005), so when the ache tracks with head position the exam moves to the cervical spine. Pain between the shoulder blades covers both patterns.
Thoracic facet and rib joints. A deep, one-sided ache beside the spine, worse twisting or arching, tender over one segment. The costotransverse joints, where the ribs meet the spine, produced that kind of local, dull ache when injected in volunteers, without wrapping around the chest (Young 2008). In one interventional series, controlled blocks confirmed the facet joints in 42% of patients with chronic thoracic pain, and a single lidocaine block was falsely positive 55% of the time (Manchikanti 2004). A thoracic medial branch block confirms the joint before ablation treats it.
Intercostal neuralgia. A burning or electric band that starts beside the spine and wraps along one rib, worse with a deep breath, with skin that stings under a shirt. It usually follows chest or breast surgery, shingles, or a rib injury. The heart and lungs are cleared first. Then an image-guided intercostal nerve block confirms and treats it. See intercostal neuralgia and, after chest surgery, post-thoracotomy pain syndrome.
Notalgia paresthetica. An itch more than a pain, fixed in one patch beside a shoulder blade, often with brownish skin from years of scratching. It is a sensory neuropathy of the upper thoracic nerve branches, which is why skin creams usually fail. Notalgia paresthetica explains the spine connection.
Thoracic disc. Common on MRI, rarely the cause. Among 90 people with no thoracic symptoms, 37% had a thoracic disc herniation and 29% some deformation of the spinal cord (Wood 1995). A symptomatic disc causes band-like pain at its level, which can respond to a thoracic epidural, or, when it presses on the cord, leg stiffness and an unsteady walk, which is a surgical question.
Compression fracture. Sudden mid-back pain after a minor fall or a hard cough, in an older adult or someone with osteoporosis or on long-term steroids, is a compression fracture until an X-ray says otherwise. Among red flags for spinal fracture, prolonged steroid use carried a 33% post-test probability, a visible bruise or abrasion 62%, and several flags together 90% (Downie 2013). It needs imaging the same day and its own track of care, including the bone-health workup.
Red flags: when to go to the emergency room instead
A few findings skip every step on this page. Go to the closest emergency room or call 911 for back pain with any of these:
- New trouble passing urine, loss of bladder or bowel control, or numbness in the groin and inner thighs (possible cauda equina syndrome)
- Leg weakness that is getting worse, or a foot that has started to drag
- Fever or chills, especially with a recent infection, a weakened immune system, or intravenous drug use
- A significant fall, car accident, or other trauma
- New back pain in someone who has had cancer
- Sudden, severe, or tearing pain between the shoulder blades, or mid-back pain with chest pressure, shortness of breath, or sweating
Most red flags on standard checklists barely move the odds alone. In a systematic review, a prior cancer was the strongest single signal for spinal malignancy, at a 33% post-test probability (Downie 2013).
Your first visit, and whether you need an MRI
The new-patient visit runs 45 to 60 minutes, all of it with Dr. Movshis. About ten minutes of history come first, then the exam: standing for motion and gait, seated for reflexes and the strength of each lumbar root (lifting the foot for L4, the big toe for L5, rising onto the toes for S1), lying down for the straight-leg raise and the SI tests, and face down for facet loading and palpation. Your MRI then goes on the screen and is read against the exam, level by level. You leave with the likely source, the test or treatment that follows, and a written plan.
Bring the images themselves, on a disc or through the imaging portal, not only the report, which often leaves out findings that change a plan, such as modest foraminal narrowing. Bring a one-page timeline of what you tried and what each thing did, and the medications with doses and results. “Ibuprofen” says little. “Ibuprofen 400 mg three times a day for ten days, mild benefit, then a steroid taper that worked for three days” says a lot, because a clear steroid response points toward inflammation and makes an epidural a reasonable next step.
Most people do not need an MRI to start. The American College of Physicians advises imaging low back pain only for severe or progressive neurologic deficits or signs of a serious underlying condition, because routine imaging adds no meaningful benefit and can cause harm (Chou 2011). An MRI earns its place when an epidural or surgery is planned and the level has to be confirmed. As a guide to what hurts, it is weak. Across 3,110 people with no back pain, disc degeneration appeared in 37% at age 20 and 96% at 80, and disc bulges in 30% and 84% (Brinjikji 2015).
A procedure, if indicated, is a separate visit booked after our office verifies benefits and clears any prior authorization, usually within one to two weeks. It takes 20 to 30 minutes under fluoroscopic or ultrasound guidance, most people are back at a desk that afternoon, and a follow-up about two weeks later sets the next step.
The non-surgical treatment ladder
Movement and exercise first. For acute low back pain, the American College of Physicians recommends noninvasive care first (heat, massage, acupuncture, or spinal manipulation), with an anti-inflammatory or a muscle relaxant if medication is wanted. For chronic pain it leads with exercise, rehabilitation, acupuncture, or mindfulness-based stress reduction, and it ranks NSAIDs as the first medication and opioids last (Qaseem 2017). Across 249 trials, exercise reduced chronic low back pain by a clinically important margin compared with no treatment or usual care (Hayden 2021). Physical therapy runs through nearly every plan here.
Then a procedure aimed at a confirmed target. A Lancet review found inappropriately high use of imaging, rest, opioids, spinal injections, and surgery for back pain worldwide (Foster 2018). The fix is aiming injections at a named structure, not avoiding them. The guide to the best injection for lower back pain sets the options side by side.
Then maintenance. A good ablation lasts many months and can be repeated when the nerve regrows, and patients with a procedural plan usually return every three to six months.
When surgery is the right referral
Dr. Movshis does not operate, which makes the surgical question easier to answer straight. These go to a spine surgeon with the exam and any block results attached:
- Cauda equina syndrome, as an emergency
- Progressing weakness, such as a worsening foot drop
- Spinal cord compression, from a thoracic disc or anywhere else
- Instability on imaging, from a fracture or a slipping vertebra
- Sciatica or stenosis that stays disabling after a real non-surgical course
- SI joint pain that keeps returning after ablation, for a minimally invasive fusion opinion
In 283 patients with six to twelve weeks of severe sciatica, early surgery relieved leg pain faster, but first-year disability did not differ, 39% of the conservative group had surgery eventually, and 95% of both groups reported recovery at one year (Peul 2007). Surgery bought speed. In stenosis, decompression beat nonsurgical care on every primary outcome at two years in the as-treated analysis, while the intention-to-treat difference was limited to bodily pain (Weinstein 2008). If pain persists after surgery, post-laminectomy syndrome covers the usual causes.
Getting to the office
Modal Pain Management is at 369 Lexington Avenue, Floor 25, New York, NY 10017, at 41st Street, two blocks south of Grand Central. The 4, 5, 6, 7, and S trains stop there, and Metro-North makes it a direct trip from Westchester and Connecticut. Same-week new-patient appointments are routinely available. Call (646) 290-6660 or book a consultation online.
Coverage and cost
Modal Pain Management accepts most commercial PPO plans, including Aetna, Anthem Blue Cross Blue Shield, Cigna, Empire Blue Cross Blue Shield, the Empire Plan, Oscar, Oxford, UMR and UnitedHealthcare. Modal Pain Management does not accept Medicare, Medicaid, HMO plans, or workers’ compensation. Our office handles prior authorization, and you can verify your insurance before the visit. Self-pay prices are flat and all-inclusive: $250 for the consultation, $1,000 for a lower-back epidural (each extra transforaminal level adds $500) or a lumbar medial branch block, $700 for an SI joint injection, and $1,500 for radiofrequency ablation of up to three lumbar levels or of the SI joint. The full list is on the self-pay pricing page.
If your back has had the rest, the stretching, the physical therapy, and the MRI, and nobody has named the structure, that is the visit to book.
References
- Hartvigsen J, Hancock MJ, Kongsted A, et al. What low back pain is and why we need to pay attention. Lancet. 2018;391(10137):2356–2367. doi:10.1016/S0140-6736(18)30480-X · PubMed
- da C Menezes Costa L, Maher CG, Hancock MJ, McAuley JH, Herbert RD, Costa LOP. The prognosis of acute and persistent low-back pain: a meta-analysis. CMAJ. 2012;184(11):E613–E624. doi:10.1503/cmaj.111271 · PubMed
- DePalma MJ, Ketchum JM, Saullo T. What is the source of chronic low back pain and does age play a role? Pain Med. 2011;12(2):224–233. doi:10.1111/j.1526-4637.2010.01045.x · PubMed
- DePalma MJ, Ketchum JM, Saullo TR. Etiology of chronic low back pain in patients having undergone lumbar fusion. Pain Med. 2011;12(5):732–739. doi:10.1111/j.1526-4637.2011.01098.x · PubMed
- Cohen SP, Raja SN. Pathogenesis, diagnosis, and treatment of lumbar zygapophysial (facet) joint pain. Anesthesiology. 2007;106(3):591–614. doi:10.1097/00000542-200703000-00024 · PubMed
- Dreyfuss P, Halbrook B, Pauza K, Joshi A, McLarty J, Bogduk N. Efficacy and validity of radiofrequency neurotomy for chronic lumbar zygapophysial joint pain. Spine (Phila Pa 1976). 2000;25(10):1270–1277. doi:10.1097/00007632-200005150-00012 · PubMed
- Cohen SP, Bhaskar A, Bhatia A, et al. Consensus practice guidelines on interventions for lumbar facet joint pain from a multispecialty, international working group. Reg Anesth Pain Med. 2020;45(6):424–467. doi:10.1136/rapm-2019-101243 · PubMed
- Laslett M, Aprill CN, McDonald B, Young SB. Diagnosis of sacroiliac joint pain: validity of individual provocation tests and composites of tests. Man Ther. 2005;10(3):207–218. doi:10.1016/j.math.2005.01.003 · PubMed
- Schwarzer AC, Aprill CN, Bogduk N. The sacroiliac joint in chronic low back pain. Spine (Phila Pa 1976). 1995;20(1):31–37. doi:10.1097/00007632-199501000-00007 · PubMed
- Chou R, Hashimoto R, Friedly J, et al. Epidural corticosteroid injections for radiculopathy and spinal stenosis: a systematic review and meta-analysis. Ann Intern Med. 2015;163(5):373–381. doi:10.7326/M15-0934 · PubMed
- Suri P, Rainville J, Kalichman L, Katz JN. Does this older adult with lower extremity pain have the clinical syndrome of lumbar spinal stenosis? JAMA. 2010;304(23):2628–2636. doi:10.1001/jama.2010.1833 · PubMed
- Kuniya H, Aota Y, Kawai T, Kaneko K, Konno T, Saito T. Prospective study of superior cluneal nerve disorder as a potential cause of low back pain and leg symptoms. J Orthop Surg Res. 2014;9:139. doi:10.1186/s13018-014-0139-7 · PubMed
- Briggs AM, Bragge P, Smith AJ, Govil D, Straker LM. Prevalence and associated factors for thoracic spine pain in the adult working population: a literature review. J Occup Health. 2009;51(3):177–192. doi:10.1539/joh.k8007 · PubMed
- Slipman CW, Plastaras C, Patel R, et al. Provocative cervical discography symptom mapping. Spine J. 2005;5(4):381–388. doi:10.1016/j.spinee.2004.11.012 · PubMed
- Young BA, Gill HE, Wainner RS, Flynn TW. Thoracic costotransverse joint pain patterns: a study in normal volunteers. BMC Musculoskelet Disord. 2008;9:140. doi:10.1186/1471-2474-9-140 · PubMed
- Manchikanti L, Boswell MV, Singh V, Pampati V, Damron KS, Beyer CD. Prevalence of facet joint pain in chronic spinal pain of cervical, thoracic, and lumbar regions. BMC Musculoskelet Disord. 2004;5:15. doi:10.1186/1471-2474-5-15 · PubMed
- Wood KB, Garvey TA, Gundry C, Heithoff KB. Magnetic resonance imaging of the thoracic spine: evaluation of asymptomatic individuals. J Bone Joint Surg Am. 1995;77(11):1631–1638. doi:10.2106/00004623-199511000-00001 · PubMed
- Downie A, Williams CM, Henschke N, et al. Red flags to screen for malignancy and fracture in patients with low back pain: systematic review. BMJ. 2013;347:f7095. doi:10.1136/bmj.f7095 · PubMed
- Chou R, Qaseem A, Owens DK, Shekelle P. Diagnostic imaging for low back pain: advice for high-value health care from the American College of Physicians. Ann Intern Med. 2011;154(3):181–189. doi:10.7326/0003-4819-154-3-201102010-00008 · PubMed
- Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR Am J Neuroradiol. 2015;36(4):811–816. doi:10.3174/ajnr.A4173 · PubMed
- Qaseem A, Wilt TJ, McLean RM, et al. Noninvasive treatments for acute, subacute, and chronic low back pain: a clinical practice guideline from the American College of Physicians. Ann Intern Med. 2017;166(7):514–530. doi:10.7326/M16-2367 · PubMed
- Hayden JA, Ellis J, Ogilvie R, Malmivaara A, van Tulder MW. Exercise therapy for chronic low back pain. Cochrane Database Syst Rev. 2021;9(9):CD009790. doi:10.1002/14651858.CD009790.pub2 · PubMed
- Foster NE, Anema JR, Cherkin D, et al. Prevention and treatment of low back pain: evidence, challenges, and promising directions. Lancet. 2018;391(10137):2368–2383. doi:10.1016/S0140-6736(18)30489-6 · PubMed
- Peul WC, van Houwelingen HC, van den Hout WB, et al. Surgery versus prolonged conservative treatment for sciatica. N Engl J Med. 2007;356(22):2245–2256. doi:10.1056/NEJMoa064039 · PubMed
- Weinstein JN, Tosteson TD, Lurie JD, et al. Surgical versus nonsurgical therapy for lumbar spinal stenosis. N Engl J Med. 2008;358(8):794–810. doi:10.1056/NEJMoa0707136 · PubMed