A typical first headache visit: a 36-year-old who works in Midtown has had migraine since college, a few attacks a month, each stopped by a triptan. Over two years the attacks crept up. Now there is some headache on 20 days a month, she takes a triptan on 12 of them, and on the worst days the pain starts at the back of the neck on the right and climbs over the head toward the eye. Her chart says “migraine.” By the formal criteria she may have three diagnoses stacked on top of each other — chronic migraine, medication-overuse headache, and a headache generated in the neck — and each one has a different treatment. Treating only the first is why the preventives so far have disappointed.
Dr. Alex Movshis treats headache and migraine at Modal Pain Management NYC, 369 Lexington Avenue, Floor 25, in Midtown Manhattan. He is an interventional pain physician who completed his anesthesiology residency at The Mount Sinai Hospital and his interventional pain medicine fellowship at the Icahn School of Medicine at Mount Sinai, and he holds dual ABA board certification in Anesthesiology and Pain Medicine. This page covers how each headache type is defined, which headaches are emergencies, and which procedure fits which diagnosis.
Name the headache first: eight diagnoses and what defines them
Headache treatment starts with the diagnosis, not the prescription. The International Classification of Headache Disorders, 3rd edition (ICHD-3), defines each headache by how long an attack lasts, what the pain is like, and what comes with it, and those definitions decide which treatment has evidence behind it.
| Diagnosis | What defines it (ICHD-3) | Where treatment starts |
|---|---|---|
| Migraine without aura | Five or more attacks lasting 4–72 hours untreated, with at least two of: one-sided, pulsating, moderate or severe, worse with routine activity. Plus nausea or vomiting, or sensitivity to both light and sound. | Acute and preventive medication. Procedures once attacks become frequent. |
| Migraine with aura | Fully reversible visual, sensory, speech, or other neurological symptoms, typically spreading over 5 minutes or more, each lasting 5–60 minutes, usually followed by headache within an hour. | As for migraine. An aura that does not fully resolve needs urgent evaluation. |
| Chronic migraine | Headache on 15 or more days a month for more than 3 months, with migraine features on at least 8 of those days. | PREEMPT Botox, with occipital nerve blocks as an adjunct. |
| Medication-overuse headache | Headache on 15 or more days a month in someone with a prior headache disorder, with regular overuse of acute medication for more than 3 months. | A withdrawal plan with prevention, sometimes bridged by nerve blocks. |
| Tension-type headache | Pressing or tightening pain, usually on both sides, mild to moderate, not worsened by routine activity, with no nausea. Attacks last 30 minutes to 7 days. | Medication. Trigger point injections when a tender muscle reproduces the headache. |
| Cluster headache | Severe, strictly one-sided pain around the eye or temple lasting 15–180 minutes, with same-side tearing, a red eye, nasal congestion, a drooping eyelid, or restlessness. From one attack every other day to 8 a day. | Oxygen and triptans. A suboccipital steroid injection as a bridge. |
| Cervicogenic headache | Headache caused by a disorder of the cervical spine, shown by at least two of: onset with the neck problem, improvement with it, reduced neck motion with provocation, or abolition by a diagnostic block of a neck structure. | Third occipital nerve or medial branch blocks, then radiofrequency ablation. |
| Occipital neuralgia | Shooting or stabbing pain in the territory of the greater, lesser, or third occipital nerve, in paroxysms of seconds to minutes, with scalp tenderness or allodynia, eased temporarily by a local anesthetic block. | An occipital nerve block, which is the test and the first treatment. |
The diagnoses overlap. ICHD-3 allows chronic migraine and medication-overuse headache to be diagnosed together, and notes that around half of patients who appear to have chronic migraine revert to episodic migraine after the overused drug is withdrawn. Cervicogenic headache and occipital neuralgia are easy to file as migraine because the pain is one-sided and severe. The features ICHD-3 lists as favoring a neck source are side-locked pain, headache provoked by pressure on the neck muscles or by head movement, and pain that radiates from back to front, although none is unique to it. Headache types by location are laid out in five kinds of headaches and when to worry, and the most common mix-up is covered in how to tell migraine from tension headache.
When a headache is an emergency
Most headaches are primary: the headache is the disease. A minority are secondary, the symptom of something else, and no visit to a pain practice should delay their evaluation. The SNNOOP10 list, a review of red flags for secondary headache published in Neurology (Do 2019), is the checklist Dr. Movshis works through at a first visit:
- Systemic symptoms, including fever
- A history of cancer
- A neurological deficit, including reduced alertness
- Sudden or abrupt onset
- Onset after age 65
- A new headache, or a change in the pattern of an old one
- Headache that changes with body position
- Headache brought on by sneezing, coughing, or exercise
- Swelling of the optic disc on eye examination (papilledema)
- A progressive headache or an atypical presentation
- Pregnancy or the weeks after delivery
- A painful eye with autonomic features such as redness or tearing
- Onset after a head injury
- An immune system disorder such as HIV
- Painkiller overuse, or a new drug started when the headache began
A headache that reaches full force almost instantly, or one that comes with fever, new weakness or numbness, confusion, trouble speaking, or loss of vision, is not an office problem. Call 911 or go to the nearest emergency room. Red flags that are not acute, such as a pattern that has been changing for months, are worked up at the first visit, and imaging is ordered before any procedure when the history or examination calls for it.
How migraine becomes chronic, and why medication overuse matters
Chronic migraine affects 1–2% of the general population and about 8% of people with migraine. Episodic migraine converts to chronic at roughly 3% a year, and the change can reverse: about 26% of patients with chronic migraine go into remission within two years (May 2016). In a systematic review of 17 studies, the strongest evidence was for a high number of headache days, depression, and overuse of acute medication (Buse 2019). Obesity, caffeine overuse, stressful life events, sleep disorders, and cutaneous allodynia, meaning scalp and skin that hurt to the touch during an attack, have supporting data as well (Bigal 2009). Female sex and acute treatment that does not work also raise the risk (May 2016). Most of the list can be changed, which is why the first visit spends time on it.
Medication overuse is the most fixable item on that list. ICHD-3 defines medication-overuse headache by days, not doses: headache on 15 or more days a month in someone with an existing headache disorder, with a triptan, an opioid, or a combination pain reliever taken on 10 or more days a month, or acetaminophen or an NSAID on 15 or more, for more than three months. The drugs are the right ones for an attack. Taken that often, they keep the headache going. The fix is a planned reduction with prevention started at the same time, and a greater occipital nerve block can carry a patient through the harder weeks. The American Headache Society consensus on nerve blocks for headache lists the transition out of a medication-overuse pattern as one of their goals (Blumenfeld 2013).
What the first headache visit looks like
The first visit is a consultation with Dr. Movshis that takes 45–60 minutes and may include an ultrasound exam. Bring a headache calendar for the last one to three months if you keep one, a list of every preventive and acute medication you have tried with the dose and how long you took it, and any MRI or CT reports. The history follows the ICHD-3 questions: how long an untreated attack lasts, where it starts, what comes with it, and how many days a month you take something for it.
The examination is where a pain physician adds the most to a headache workup. Dr. Movshis checks the upper neck for lost rotation and for tenderness over the C2–C3 facet joint, presses along the greater and lesser occipital nerves at the skull base for a Tinel’s sign, and looks for trigger points in the trapezius, sternocleidomastoid, and temporalis that reproduce the headache. A neurological examination covers the red flags above.
You leave with a named diagnosis, or a short list and the test that will separate them, and a plan. When a procedure is indicated it is usually scheduled separately, after benefits are verified, and typically within one to two weeks. Botox for chronic migraine needs prior authorization, which our office submits, and that usually takes 7–14 business days.
Chronic migraine: PREEMPT Botox and occipital nerve blocks
Botox (onabotulinumtoxinA) is FDA-approved to prevent headaches in adults with chronic migraine. The label dose is 155 units, given as 31 injections of 5 units across seven head and neck muscle areas and repeated every 12 weeks. The label also states that safety and effectiveness have not been established in episodic migraine, meaning 14 or fewer headache days a month. In the pooled PREEMPT trials of 1,384 adults, headache days fell by 8.4 a month at 24 weeks with Botox against 6.6 with placebo (Dodick 2010). The 2018 Cochrane review puts the placebo-adjusted benefit at 1.9 fewer headache days a month in chronic migraine, from high-quality evidence, and the one trial in episodic migraine found no difference in migraine days (Herd 2018).
Those are averages. An individual’s response is judged over two to three cycles, not after the first. The injections work on sensory nerve endings, reducing the release of CGRP and other pain-signaling molecules, rather than by relaxing muscle (Burstein 2020), and the 74-second Botox mechanism animation shows how. Eligibility, the session itself, and side effects are covered on the headache and migraine injections page and in the complete guide to Botox for chronic migraine.
Greater occipital nerve blocks are the other procedure with placebo-controlled evidence in chronic migraine. In a multicenter trial, four weekly blocks with bupivacaine lowered headache days from 18.1 to 8.8 a month, against 16.9 to 13.2 with saline (Inan 2015). A block wears off and is repeated. It earns its place while Botox builds over the first cycles, and, case by case, as a bridge off overused medication.
Headache that starts in the neck: diagnostic blocks, then radiofrequency ablation
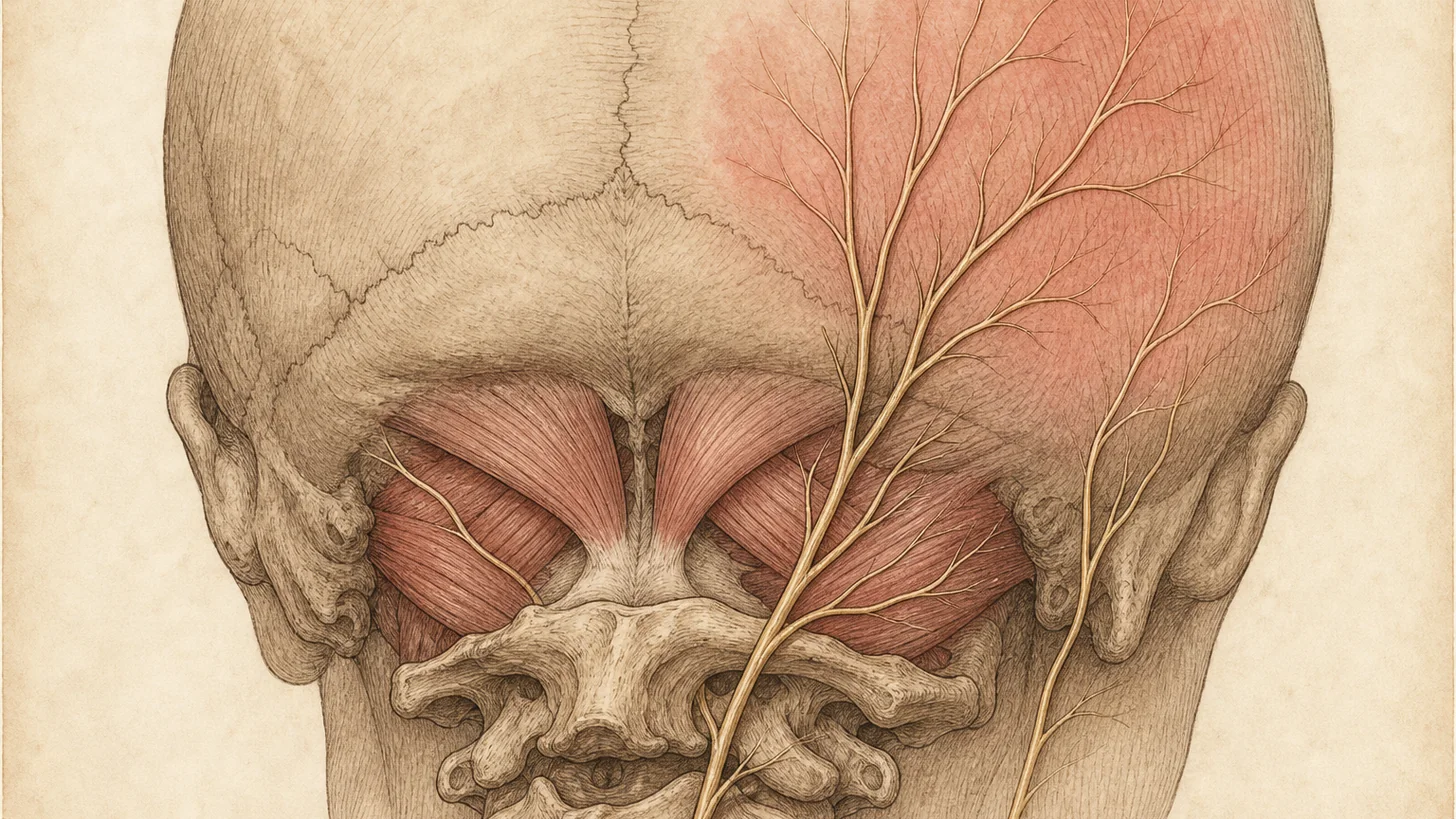
Cervicogenic headache is referred pain: laboratory and clinical studies have shown that pain from the upper cervical joints and muscles can be felt in the head (Bogduk 2009). Imaging does not make the diagnosis. No imaging finding has been shown to correlate with cervicogenic headache (Haldeman 2001), so an MRI can rule other problems out but cannot say which joint hurts. A diagnostic block can help: if numbing the nerve that supplies a suspected joint clearly eases the headache for the life of the anesthetic, that joint is the likely source (Bogduk 2009). In 166 consecutive patients with probable cervicogenic headache, controlled blocks identified the source in 75% of those whose main complaint was headache, and the C2–C3 joint was responsible in 62% (Govind 2022). That joint is supplied by the third occipital nerve.
When diagnostic blocks point to the joint, radiofrequency ablation of the third occipital nerve can give relief measured in months. In an uncontrolled series of 49 patients from the group that developed the technique, all diagnosed with controlled blocks, 88% had complete relief lasting at least 90 days. In those responders relief lasted a median of 297 days, about 10 months, and a repeat procedure restored relief in 12 of 14 (Govind 2003). There was no sham group. In a retrospective 40-patient series from another center, which included occipital neuralgia and also treated the C2 dorsal root ganglion, improvement lasted about 5 months on average (Hamer 2014). Dr. Movshis performs third occipital nerve blocks with ultrasound and cervical medial branch blocks under fluoroscopy in the office, and the same joints are covered from the neck-pain side on the neck pain page. The 66-second cervicogenic headache animation shows how a neck joint refers pain into the head, and the cervicogenic headache guide covers the symptoms in more depth.
Occipital neuralgia, cluster headache, and tension-type headache
Occipital neuralgia. The clinical pattern above ends at its treatment: an occipital nerve block with local anesthetic is both the test and the first treatment, and the occipital nerve block page explains why steroid is usually left out. The occipital neuralgia guide covers the condition, and the occipital nerve block page covers repeat intervals and what comes next when blocks stop lasting. Pain along the trigeminal nerve in the face is a different problem, covered on the facial and cranial nerve pain page.
Cluster headache. Attacks are treated with oxygen and triptans. High-flow oxygen at 12 liters a minute by face mask left 78% of attacks pain-free at 15 minutes, against 20% with air (Cohen 2009), and triptans are the most effective drugs for the attack itself (Hoffmann 2018). Preventive medication is usually managed by a neurologist. A procedure’s job is to shorten the bout while prevention takes hold. In a randomized trial of patients having more than two attacks a day, three suboccipital steroid injections added to verapamil brought 20 of 21 patients down to two or fewer attacks a day, against 12 of 22 on placebo (Leroux 2011). A transnasal sphenopalatine ganglion block, placed in the office through a thin catheter with no needle, is also available. Its evidence is thinner: a 38-patient pilot trial in chronic migraine found lower pain scores with repeated bupivacaine blocks (Cady 2015), and the 2025 American Headache Society guideline found too little evidence to recommend it for an acute migraine attack (Robblee 2025).
Tension-type headache. It is the most prevalent neurological disorder in the world (Ashina 2021). Simple analgesics treat the attacks, and frequent or chronic tension-type headache is prevented with medication such as amitriptyline. An American Headache Society consensus supports trigger point injections as an adjunct when the examination finds an active trigger point, most often in the trapezius, sternocleidomastoid, or temporalis (Robbins 2014).
An attack in progress: the in-office IV instead of the ER
For an attack your usual medication has not stopped, the in-office migraine cocktail IV delivers ketorolac and metoclopramide with magnesium and fluids. The 2025 American Headache Society guideline on emergency department migraine care rates IV ketorolac and IV metoclopramide as treatments that should be offered, and a greater occipital nerve block as one that must be offered to eligible adults (Robblee 2025). Dr. Movshis reviews your history and medications first, the infusion runs about 45–60 minutes in a quiet room, and because it is self-pay there is no referral or authorization to wait on.
It is a rescue, not a prevention plan. Needing it more than occasionally is a sign the preventive side needs work. And it does not apply to a headache with the warning signs above. For those, call 911 or go to the nearest emergency room.
How procedures fit with your neurologist’s plan
Preventive medication is the foundation for most people with frequent migraine: the older oral classes, and the drugs that target calcitonin gene-related peptide (CGRP), which include monoclonal antibodies given by injection or infusion and the oral gepants. A neurologist or primary care doctor usually prescribes and adjusts them. Procedures add to that plan when medication has not been enough or cannot be tolerated. They do not replace it. Dr. Movshis sends notes to your neurologist or primary care doctor after each visit, and neurologists can refer patients directly for the procedures alone.
For headaches that have not responded to medication, Botox, or blocks, implanted occipital nerve stimulation has been tested. A multicenter sham-controlled trial in 157 patients with chronic migraine missed its primary endpoint, although headache days fell more with active stimulation, and the most common adverse event was persistent pain at the implant site (Silberstein 2012). Modal Pain Management NYC does not implant stimulators, and the rare patient who reaches that point is referred to an implanting specialist for an evaluation.
Coverage and self-pay cost
Modal Pain Management NYC accepts most commercial PPO plans, including Aetna, Anthem Blue Cross Blue Shield, Cigna, Empire Blue Cross Blue Shield, the Empire Plan, Oscar, Oxford, UMR and UnitedHealthcare, and does not accept Medicare, Medicaid, HMO plans, or workers’ compensation. Coverage for occipital nerve blocks and trigger point injections varies by plan and diagnosis, and our office checks your plan’s policy first. Botox for chronic migraine needs prior authorization, each plan sets its own criteria, and what those usually ask for is explained in does insurance cover Botox for migraines. Self-pay prices are flat and published: a new-patient consultation is $250, an occipital nerve block $500, and a PREEMPT Botox session $2,000, with the rest on the self-pay pricing page. You can verify your insurance before the visit.
If you take something for headache on 10 or more days a month, or your “migraine” starts in your neck, that is the visit to book.
References
- Headache Classification Committee of the International Headache Society (IHS). The International Classification of Headache Disorders, 3rd edition. Cephalalgia. 2018;38(1):1–211. doi:10.1177/0333102417738202 · PubMed
- Dougherty C. Occipital neuralgia. Curr Pain Headache Rep. 2014;18(5):411. doi:10.1007/s11916-014-0411-x · PubMed
- Do TP, Remmers A, Schytz HW, et al. Red and orange flags for secondary headaches in clinical practice: SNNOOP10 list. Neurology. 2019;92(3):134–144. doi:10.1212/WNL.0000000000006697 · PubMed
- May A, Schulte LH. Chronic migraine: risk factors, mechanisms and treatment. Nat Rev Neurol. 2016;12(8):455–464. doi:10.1038/nrneurol.2016.93 · PubMed
- Buse DC, Greisman JD, Baigi K, Lipton RB. Migraine progression: a systematic review. Headache. 2019;59(3):306–338. doi:10.1111/head.13459 · PubMed
- Bigal ME, Lipton RB. What predicts the change from episodic to chronic migraine? Curr Opin Neurol. 2009;22(3):269–276. doi:10.1097/WCO.0b013e32832b2387 · PubMed
- Blumenfeld A, Ashkenazi A, Napchan U, et al. Expert consensus recommendations for the performance of peripheral nerve blocks for headaches — a narrative review. Headache. 2013;53(3):437–46. doi:10.1111/head.12053 · PubMed
- BOTOX (onabotulinumtoxinA) for injection — US Prescribing Information, sections 1 (Indications) and 2 (Dosage and Administration), chronic migraine. Allergan, Inc. (an AbbVie company). DailyMed, U.S. National Library of Medicine. DailyMed
- Dodick DW, Turkel CC, DeGryse RE, et al. OnabotulinumtoxinA for treatment of chronic migraine: pooled results from the double-blind, randomized, placebo-controlled phases of the PREEMPT clinical program. Headache. 2010;50(6):921–36. doi:10.1111/j.1526-4610.2010.01678.x · PubMed
- Herd CP, Tomlinson CL, Rick C, et al. Botulinum toxins for the prevention of migraine in adults. Cochrane Database Syst Rev. 2018;6(6):CD011616. doi:10.1002/14651858.CD011616.pub2 · PubMed
- Burstein R, Blumenfeld AM, Silberstein SD, Manack Adams A, Brin MF. Mechanism of Action of OnabotulinumtoxinA in Chronic Migraine: A Narrative Review. Headache. 2020;60(7):1259–1272. doi:10.1111/head.13849 · PubMed
- Inan LE, Inan N, Karadaş Ö, et al. Greater occipital nerve blockade for the treatment of chronic migraine: a randomized, multicenter, double-blind, and placebo-controlled study. Acta Neurol Scand. 2015;132(4):270–7. doi:10.1111/ane.12393 · PubMed
- Bogduk N, Govind J. Cervicogenic headache: an assessment of the evidence on clinical diagnosis, invasive tests, and treatment. Lancet Neurol. 2009;8(10):959–68. doi:10.1016/S1474-4422(09)70209-1 · PubMed
- Haldeman S, Dagenais S. Cervicogenic headaches: a critical review. Spine J. 2001;1(1):31–46. doi:10.1016/S1529-9430(01)00024-9 · PubMed
- Govind J, Bogduk N. Sources of cervicogenic headache among the upper cervical synovial joints. Pain Med. 2022;23(6):1059–1065. doi:10.1093/pm/pnaa469 · PubMed
- Govind J, King W, Bailey B, Bogduk N. Radiofrequency neurotomy for the treatment of third occipital headache. J Neurol Neurosurg Psychiatry. 2003;74(1):88–93. doi:10.1136/jnnp.74.1.88 · PubMed
- Hamer JF, Purath TA. Response of cervicogenic headaches and occipital neuralgia to radiofrequency ablation of the C2 dorsal root ganglion and/or third occipital nerve. Headache. 2014;54(3):500–10. doi:10.1111/head.12295 · PubMed
- Cohen AS, Burns B, Goadsby PJ. High-flow oxygen for treatment of cluster headache: a randomized trial. JAMA. 2009;302(22):2451–7. doi:10.1001/jama.2009.1855 · PubMed
- Hoffmann J, May A. Diagnosis, pathophysiology, and management of cluster headache. Lancet Neurol. 2018;17(1):75–83. doi:10.1016/S1474-4422(17)30405-2 · PubMed
- Leroux E, Valade D, Taifas I, et al. Suboccipital steroid injections for transitional treatment of patients with more than two cluster headache attacks per day: a randomised, double-blind, placebo-controlled trial. Lancet Neurol. 2011;10(10):891–7. doi:10.1016/S1474-4422(11)70186-7 · PubMed
- Cady R, Saper J, Dexter K, Manley HR. A double-blind, placebo-controlled study of repetitive transnasal sphenopalatine ganglion blockade with Tx360 as acute treatment for chronic migraine. Headache. 2015;55(1):101–16. doi:10.1111/head.12458 · PubMed
- Robblee J, Minen MT, Friedman BW, et al. 2025 guideline update to acute treatment of migraine for adults in the emergency department: the American Headache Society evidence assessment of parenteral pharmacotherapies. Headache. 2025;66(1):53–76. doi:10.1111/head.70016 · PubMed
- Ashina S, Mitsikostas DD, Lee MJ, et al. Tension-type headache. Nat Rev Dis Primers. 2021;7(1):24. doi:10.1038/s41572-021-00257-2 · PubMed
- Robbins MS, Kuruvilla D, Blumenfeld A, et al. Trigger point injections for headache disorders: expert consensus methodology and narrative review. Headache. 2014;54(9):1441–59. doi:10.1111/head.12442 · PubMed
- Silberstein SD, Dodick DW, Saper J, et al. Safety and efficacy of peripheral nerve stimulation of the occipital nerves for the management of chronic migraine: results from a randomized, multicenter, double-blinded, controlled study. Cephalalgia. 2012;32(16):1165–79. doi:10.1177/0333102412462642 · PubMed