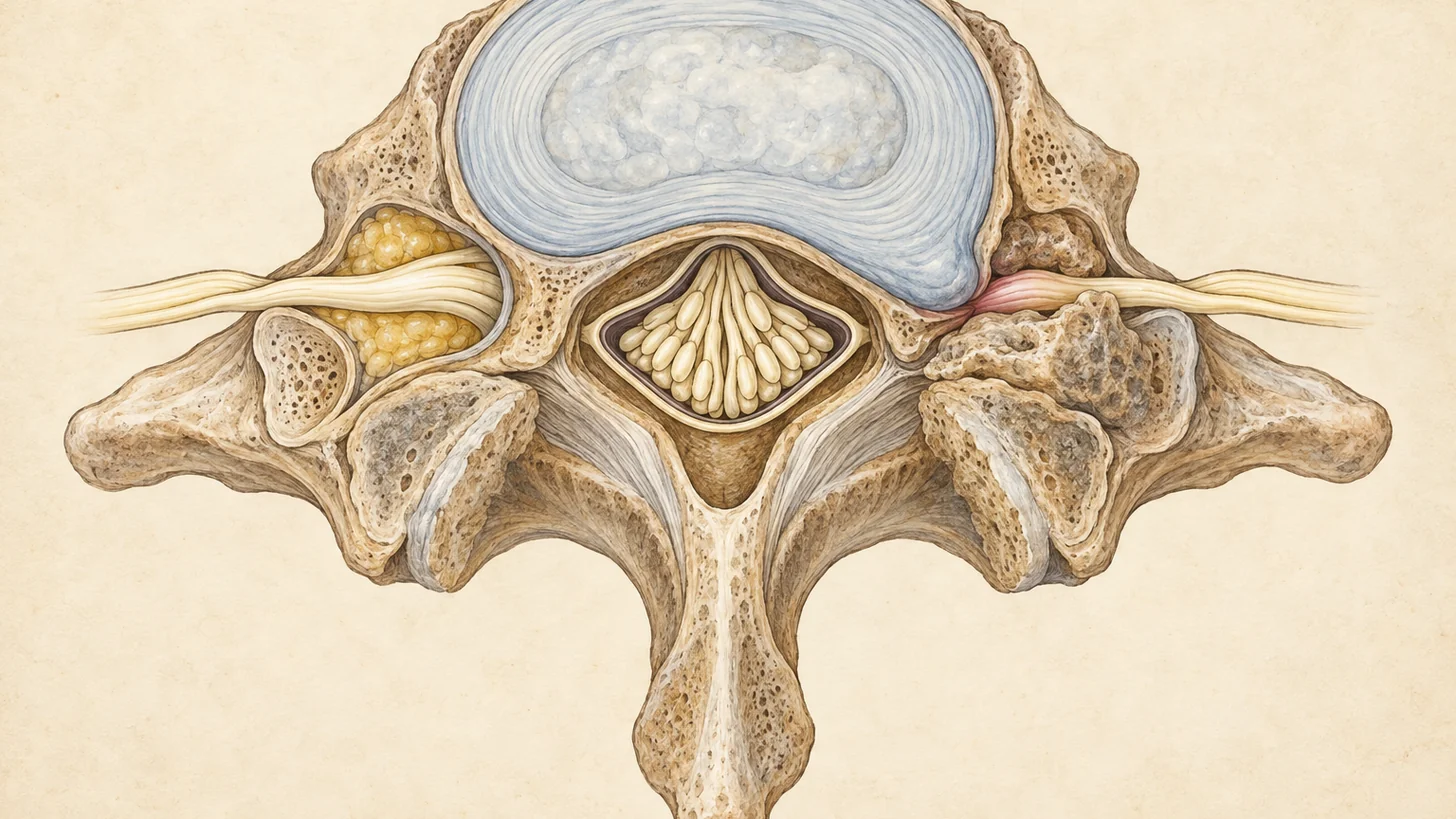
At Modal Pain Management NYC, we specialize in precision nerve block treatments under the care of Dr. Alex Movshis, a board-certified interventional pain physician. Nerve blocks are versatile procedures that interrupt pain signals traveling from an injured area to the brain, providing targeted relief without surgery. By blocking specific nerves with carefully placed injections, we can achieve significant pain reduction while preserving other sensations and motor function. Nerve blocks serve dual purposes in our practice: diagnostically, they help pin down the source of your pain, and therapeutically, they can provide relief that helps you to return to daily activities and participate fully in rehabilitation. Whether you’re managing acute pain from recent injury or chronic pain from longstanding conditions, nerve blocks offer a minimally invasive pathway to meaningful relief in the New York City area.
How Nerve Blocks Work
Nerve blocks function by delivering local anesthetic medication directly to the nerve or nerve cluster responsible for transmitting pain signals from your affected area. When the anesthetic reaches the nerve, it temporarily blocks the electrical signals that the nerve uses to communicate pain sensations to the brain. Our team uses advanced ultrasound or fluoroscopic guidance to ensure the medication reaches the precise location, maximizing effectiveness while minimizing discomfort. Different types of anesthetics are selected based on the desired duration of relief and your specific condition. Some anesthetics provide relief lasting hours to days, making them ideal for diagnostic purposes, while others combine longer-acting medications that extend relief for weeks or even months. The procedure itself typically takes between ten and thirty minutes depending on the complexity and type of nerve block being performed. Dr. Movshis personalizes each treatment plan, selecting the anesthetic combination that best serves your pain management goals.
Types of Nerve Blocks We Offer
Our nerve block offerings address pain across different regions of the body. Occipital nerve blocks target headaches and migraines by blocking nerves at the base of the skull, providing relief for patients who have exhausted other treatment options. Stellate ganglion blocks address pain in the upper extremities, chest, and head by blocking the sympathetic nervous system’s role in pain transmission. Intercostal nerve blocks treat pain along the ribcage and chest wall, commonly used for post-surgical pain, rib fractures, and thoracic conditions. Medial branch blocks test whether the small facet joints of the spine are the source of back or neck pain, which decides whether radiofrequency ablation is worth considering (Cohen 2020). Peripheral nerve blocks address pain in the arms, legs, hands, and feet by blocking individual nerves that supply those areas. Each block type serves specific anatomical regions and conditions, and our diagnostic evaluation determines which approach will be most effective for your particular pain problem.
Conditions Treated
Nerve blocks are used for a wide range of acute and chronic pain conditions. Chronic headaches and migraines, particularly those resistant to preventive medications, often respond to occipital nerve blocks, though outside cluster headache the evidence is limited (Blumenfeld 2013). Back and neck pain from facet joint arthritis can be tested with medial branch blocks, while nerve root pain from a disc herniation is treated with other spinal injections. Patients experiencing complex regional pain syndrome, a condition involving limb pain disproportionate to the initial injury, frequently benefit from sympathetic nerve blocks. Post-operative pain management represents another important application, keeping patients comfortable enough for physical therapy during recovery. Modal Pain does not prescribe opioids. Additionally, nerve blocks address peripheral neuropathy pain, shingles pain, and pain from conditions like reflex sympathetic dystrophy. Our diagnostic nerve blocks help establish which nerves are responsible for your pain, ensuring subsequent therapeutic injections target the correct structures.
What to Expect During the Procedure
When you arrive for your nerve block procedure at our NYC facility, you’ll be positioned comfortably to allow Dr. Movshis access to the target nerve or nerve cluster. The skin over the injection site is cleaned thoroughly and typically numbed with a small amount of topical anesthetic. Using real-time ultrasound or fluoroscopic imaging, Dr. Movshis carefully advances the needle to the precise location of the nerve, ensuring accurate placement while minimizing tissue trauma. Once the needle position is confirmed through imaging, the anesthetic medication is delivered slowly to block nerve conduction. Most patients report minimal discomfort during the injection itself, particularly given the numbing effect of the topical anesthetic. After the procedure, you’ll rest briefly in our recovery area before being discharged home with detailed post-injection instructions. You can typically resume light activities immediately, though we recommend avoiding strenuous exercise for a few days to allow the medication to fully take effect.
Effectiveness and Results
Local anesthetic works within minutes, so many patients notice relief soon after the procedure. The effectiveness varies based on the specific condition, the accuracy of needle placement, and the type of anesthetic used. Diagnostic nerve blocks typically provide hours of relief and serve the purpose of showing which nerves are likely responsible for your pain. Therapeutic nerve blocks can last longer, from days to weeks or more in some patients, and the duration varies widely. Some patients enjoy complete pain relief from a single injection, while others find that periodic repeat injections maintain their improvement. This flexibility allows us to adapt treatment to your body’s response and your evolving pain management needs. Following the block, many patients report not only pain reduction but also improved function, allowing them to participate in physical therapy and resume activities they previously had to avoid.
Treatment Planning
Dr. Movshis develops individualized treatment plans based on your specific pain diagnosis, medical history, and treatment goals. Before your first nerve block, we conduct thorough diagnostic imaging and physical examination to identify the exact source of your pain and confirm that you’re a suitable candidate for the procedure. If you’ve tried conservative treatments without adequate relief, a diagnostic nerve block may be recommended to test the likely pain source before committing to longer-acting therapeutic blocks. For patients with confirmed diagnoses, we discuss realistic expectations regarding pain relief duration and whether a repeat injection makes sense or, for a confirmed nerve entrapment, whether surgical referral is the better next step. We also integrate nerve blocks within a broader pain management strategy that may include physical therapy, medication adjustment, or other interventional procedures. Our goal is to provide sustainable relief that enhances your quality of life and reduces your dependence on medications with concerning side effects. Regular follow-up appointments allow us to assess your response and adjust your treatment plan as needed.
References
- Blumenfeld A, Ashkenazi A, Napchan U, et al. Expert consensus recommendations for the performance of peripheral nerve blocks for headaches — a narrative review. Headache. 2013;53(3):437–46. doi:10.1111/head.12053 · PubMed
- Cohen SP, Peterlin BL, Fulton L, et al. Randomized, double-blind, comparative-effectiveness study comparing pulsed radiofrequency to steroid injections for occipital neuralgia or migraine with occipital nerve tenderness. Pain. 2015;156(12):2585–2594. doi:10.1097/j.pain.0000000000000373 · PubMed
- Cohen SP, Bhaskar A, Bhatia A, et al. Consensus practice guidelines on interventions for lumbar facet joint pain from a multispecialty, international working group. Reg Anesth Pain Med. 2020;45(6):424–467. doi:10.1136/rapm-2019-101243 · PubMed
- Smuck M, Crisostomo RA, Trivedi K, Agrawal D. Success of initial and repeated medial branch neurotomy for zygapophysial joint pain: a systematic review. PM R. 2012;4(9):686–92. doi:10.1016/j.pmrj.2012.06.007 · PubMed