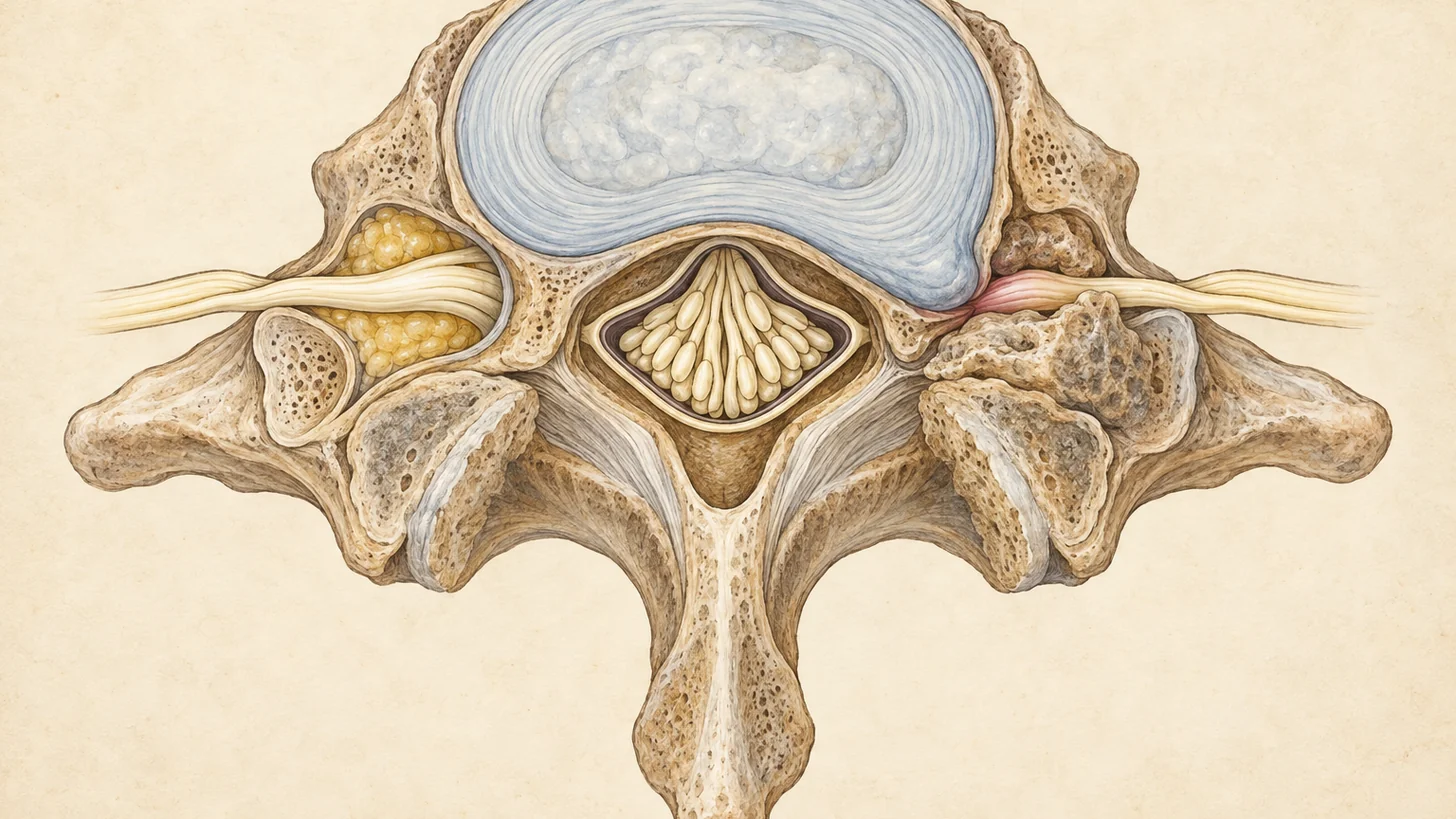
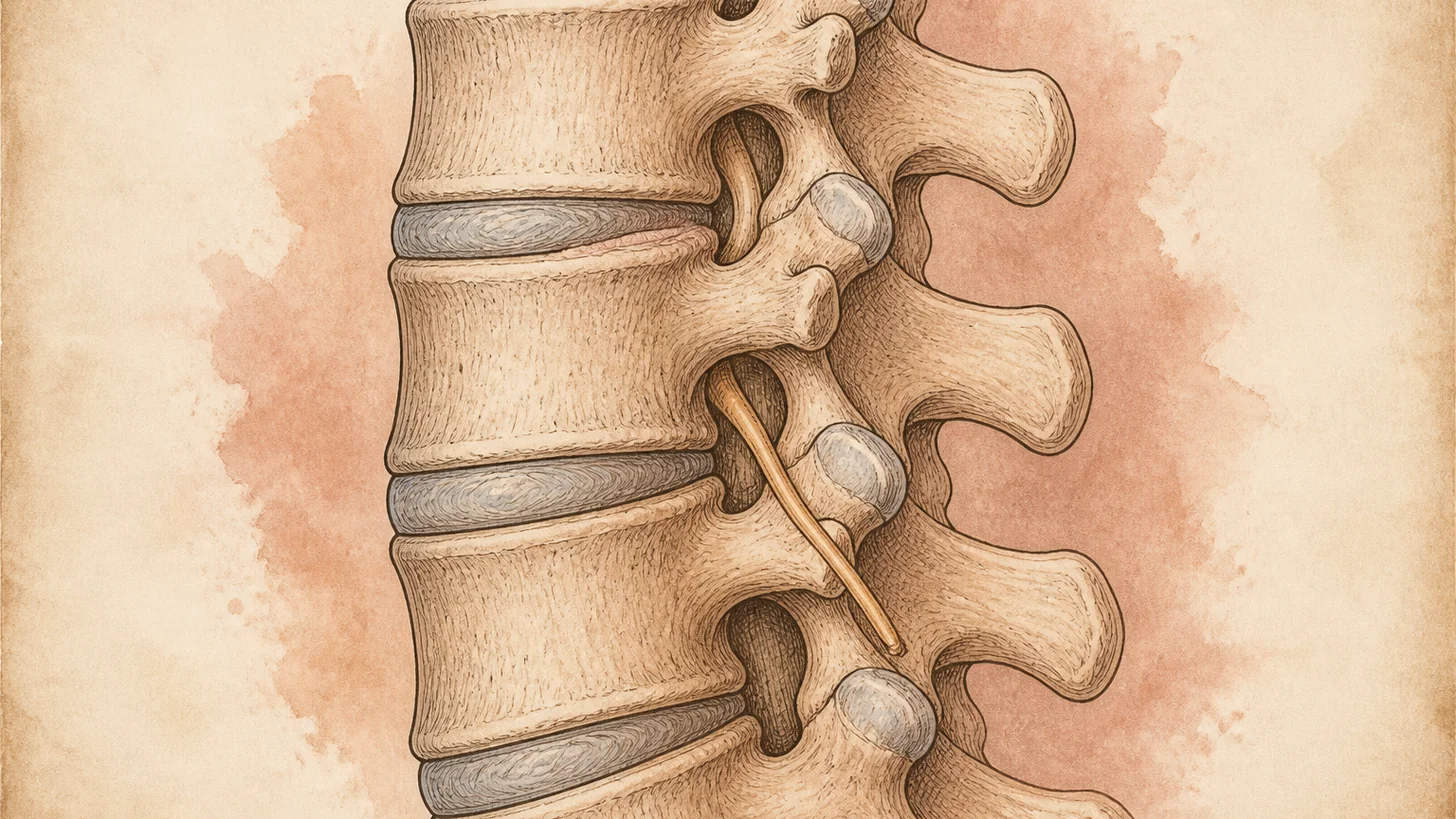
Sciatica refers to pain that radiates along the sciatic nerve pathway, typically from the lower back through the buttocks and down the leg. At Modal Pain Management NYC in Midtown Manhattan, Dr. Alex Movshis treats sciatica without surgery. Most often the cause is an irritated lumbar nerve root, from a disc herniation or a narrowed spinal canal or foramen. Less often the sciatic nerve is irritated in the buttock, as in piriformis or deep gluteal syndrome. The pain can be sharp or burning, with numbness or weakness in the leg. How common sciatica is depends on how it is defined: published estimates range from 1.2% to 43% (Konstantinou 2008). Most people improve without an operation (Peul 2007).
Prefer to watch? A 75-second narrated animation of sciatica’s three starting points — disc, piriformis muscle, or spinal canal — with the full transcript and PubMed-verified references.
Understanding Sciatic Nerve Pain
The sciatic nerve is the longest nerve in the human body, originating from the lumbar and sacral spinal nerves (L4-S3) and extending through the buttocks down to the feet. This nerve controls sensation and movement in much of the lower body, making any compression or irritation particularly disruptive to daily function. When one of the roots that form the nerve is irritated as it leaves the spine, or the nerve itself is irritated in the buttock, the pain follows the nerve’s path, sometimes all the way to the foot. Because irritation can happen at more than one point along the way, the exam has to work out where.
Common Causes of Sciatica
Sciatica can develop from several distinct conditions affecting the lumbar spine and surrounding tissues. A herniated disc in the lumbar spine is the most frequent culprit, when the soft inner material of a disc pushes outward and irritates the L4, L5, or S1 nerve root. Many herniations shrink on their own, especially extrusions and sequestrations (Chiu 2015). Spinal stenosis, a narrowing of the spinal canal often related to aging and degenerative changes, can also compress nerve roots and trigger sciatic pain. Piriformis syndrome occurs when the piriformis muscle irritates the sciatic nerve as it passes beneath or through the muscle. It belongs to a wider group called deep gluteal syndrome, in which the nerve is trapped in the buttock rather than at the spine (Martin 2015). Its four most commonly reported features are buttock pain, pain worse sitting, tenderness near the sciatic notch and pain when the muscle is stretched, but how accurate any of these is remains unknown, and how common the syndrome is among people with sciatica has not been established (Hopayian 2018). Spondylolisthesis, where one vertebra slips forward over the one below it, may also compress nerve roots and cause radiating pain. Less commonly, pelvic tumors or pregnancy-related changes can contribute to sciatic symptoms. A common mimic of upper lumbar (L2/L3) radiculopathy is meralgia paresthetica, entrapment of the lateral femoral cutaneous nerve near the hip bone that produces burning, tingling and numbness in a patch of the front and outer thigh, with no weakness and symptoms that do not cross the knee. It can lead to lumbar MRIs and epidurals before the right diagnosis is made, and an ultrasound-guided diagnostic block of that nerve can help test it. If your “sciatica” is actually a burning patch on the front of the thigh that does not extend past the knee, ask specifically about meralgia paresthetica. Our team conducts thorough evaluations to identify which specific cause is driving your symptoms.
Symptoms and When to Seek Care
Sciatic pain typically manifests as a sharp, burning, or stabbing sensation that begins in the lower back or buttocks and radiates down the leg. Many patients describe pain that follows a specific path along the nerve distribution, and symptoms may worsen with certain movements like bending forward or sitting for extended periods. Beyond pain, patients frequently experience numbness, tingling, or weakness in the affected leg and foot, which can make walking, climbing stairs, or even driving challenging. Some individuals develop foot drop, where weakness in the foot muscles makes it difficult to lift the front of the foot while walking. When sciatica persists beyond a few weeks or significantly limits your daily activities, book an evaluation. Loss of bowel or bladder control, numbness in the groin or inner thighs, or weakness that is getting worse is different: call 911 or go to the nearest emergency room, because these can signal cauda equina syndrome.
Diagnosis and Assessment
Accurate diagnosis is essential before beginning any treatment plan. During your initial consultation, Dr. Alex Movshis will conduct a full physical examination, including specific tests that reproduce or alleviate your sciatic pain. We assess your range of motion, strength, and reflexes to pinpoint the likely source of your symptoms. An MRI shows the discs, the canal and the nerve roots when the leg pain persists or a procedure is planned, but findings have to match the exam, because disc problems are common in people without pain. Some cases benefit from nerve conduction studies or electromyography to check how the nerves are working. The goal is to aim treatment at the most likely cause.
Treatment Options
Staying active comes first. Bed rest does not help sciatica, and advice to stay active does about as well (Dahm 2010). When leg pain from a nerve root stays severe, an epidural steroid injection places anti-inflammatory medication next to the root. In pooled placebo-controlled trials the benefit was small and short-term (Pinto 2012, Chou 2015), and for radicular pain lasting three months or longer a 2025 BMJ guideline panel recommended against epidural injections (Busse 2025). Nerve blocks place anesthetic around a nerve and can help with both diagnosis and treatment. For piriformis syndrome we use an ultrasound-guided piriformis injection, though the evidence for it is limited. Most people improve over weeks to a few months (Peul 2007).
What to Expect During Treatment
When you come to our clinic at 369 Lexington Avenue, Floor 25 in Midtown Manhattan, our team will prepare you for your procedure with detailed explanations of what to expect. Most interventional treatments for sciatica are performed as outpatient procedures using advanced imaging guidance to ensure precise needle placement. You’ll be positioned comfortably, and the treatment area will be cleaned and numbed before the procedure begins. The injection itself takes only a few minutes, and you may feel pressure or brief discomfort as medication is delivered. The numbing medicine can take the pain away for a few hours. The steroid works over days, and the result is judged two to four weeks later. You go home with a driver and written instructions, which are also on the epidural aftercare page.
Long-Term Outlook and Prevention
Most people with sciatica improve, and most avoid surgery. In a trial of 283 people with 6 to 12 weeks of severe sciatica who started with non-surgical care, 61% had not needed an operation by one year, and 95% of both groups reported recovery at one year (Peul 2007). In the randomized SPORT trial, surgical and non-surgical groups both improved substantially over two years, with small differences between them (Weinstein 2006). Regular exercise and staying active are sensible ways to lower the odds of another episode. A repeat injection makes sense only when an earlier one gave real relief that has worn off. Working with Dr. Alex Movshis and our team ensures you have a personalized prevention strategy tailored to your specific condition and lifestyle.
References
- Konstantinou K, Dunn KM. Sciatica: review of epidemiological studies and prevalence estimates. Spine (Phila Pa 1976). 2008;33(22):2464–72. doi:10.1097/BRS.0b013e318183a4a2 · PubMed
- Chiu CC, Chuang TY, Chang KH, Wu CH, Lin PW, Hsu WY. The probability of spontaneous regression of lumbar herniated disc: a systematic review. Clin Rehabil. 2015;29(2):184–95. doi:10.1177/0269215514540919 · PubMed
- Peul WC, van Houwelingen HC, van den Hout WB, et al. Surgery versus prolonged conservative treatment for sciatica. N Engl J Med. 2007;356(22):2245–56. doi:10.1056/NEJMoa064039 · PubMed
- Weinstein JN, Tosteson TD, Lurie JD, et al. Surgical vs nonoperative treatment for lumbar disk herniation: the Spine Patient Outcomes Research Trial (SPORT): a randomized trial. JAMA. 2006;296(20):2441–50. doi:10.1001/jama.296.20.2441 · PubMed
- Chou R, Hashimoto R, Friedly J, et al. Epidural Corticosteroid Injections for Radiculopathy and Spinal Stenosis: A Systematic Review and Meta-analysis. Ann Intern Med. 2015;163(5):373–81. doi:10.7326/M15-0934 · PubMed
- Pinto RZ, Maher CG, Ferreira ML, et al. Epidural corticosteroid injections in the management of sciatica: a systematic review and meta-analysis. Ann Intern Med. 2012;157(12):865–77. doi:10.7326/0003-4819-157-12-201212180-00564 · PubMed
- Dahm KT, Brurberg KG, Jamtvedt G, Hagen KB. Advice to rest in bed versus advice to stay active for acute low-back pain and sciatica. Cochrane Database Syst Rev. 2010;2010(6):CD007612. doi:10.1002/14651858.CD007612.pub2 · PubMed
- Martin HD, Reddy M, Gómez-Hoyos J. Deep gluteal syndrome. J Hip Preserv Surg. 2015;2(2):99–107. doi:10.1093/jhps/hnv029 · PubMed
- Hopayian K, Danielyan A. Four symptoms define the piriformis syndrome: an updated systematic review of its clinical features. Eur J Orthop Surg Traumatol. 2018;28(2):155–164. doi:10.1007/s00590-017-2031-8 · PubMed
- Busse JW, Genevay S, Agarwal A, et al. Commonly used interventional procedures for non-cancer chronic spine pain: a clinical practice guideline. BMJ. 2025;388:e079970. doi:10.1136/bmj-2024-079970 · PubMed