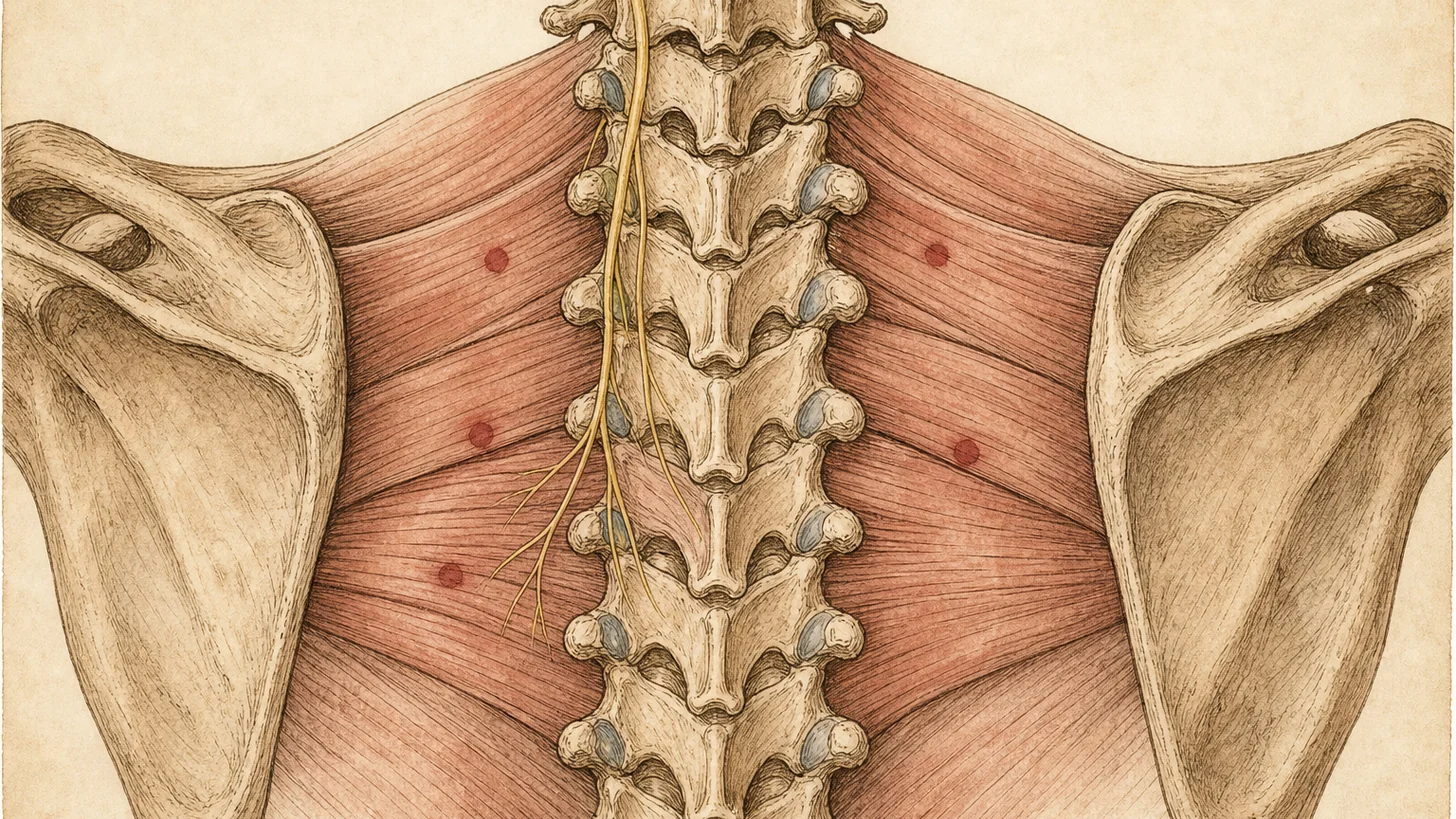
A muscle spasm is a sudden, involuntary tightening of a muscle, often painful, like a back that seizes after a lift or a calf cramp at night. Myofascial pain is related but different: an ongoing, regional ache from tight, tender bands in a muscle that reproduce your pain when pressed. At Modal Pain Management NYC, 369 Lexington Ave, Floor 25, Dr. Alex Movshis treats muscle spasm and myofascial pain in the neck, shoulders, back and buttock with an examination-led plan: trigger point injections when the exam points to a muscle, combined with stretching, strengthening and attention to whatever keeps loading that muscle.
Spasticity is a different condition. It is stiffness and overactive reflexes from damage to the brain or spinal cord, as after a stroke, a spinal cord injury or multiple sclerosis, and it is treated differently. This page does not cover it.
Understanding Myofascial Pain Syndrome
Myofascial pain syndrome is regional muscle pain with active trigger points. In 2018 an international panel of experts agreed on three core features of a trigger point: a taut band you can feel, a hypersensitive spot within that band, and referred pain when it is pressed (Fernández-de-las-Peñas 2018). An active trigger point reproduces the pain you came in with. The pain is often felt away from the trigger point, and the area it refers to does not follow a fixed map (Fernández-de-las-Peñas 2018).
Why trigger points form is still debated. The classic explanation, that a small patch of muscle fibers gets stuck in a contracted state after overload or injury, has never been proven. Small studies found higher levels of chemicals linked to pain and inflammation around active trigger points than in normal muscle, and sensitization of the nervous system may play a part (Shah 2015). Myofascial pain is different from fibromyalgia, which is widespread pain, and one review holds that long-standing myofascial pain does not turn into fibromyalgia (Gerwin 2001).
Common Causes
Overuse and sustained postures, such as long hours at a screen or repetitive work, are common starting points. So are injuries, from a fall or whiplash to a sudden awkward lift. Myofascial pain can also develop on top of another problem, such as a disc, joint or nerve condition, when the muscles guard around it (Gerwin 2001). Stress, poor sleep and low mood make the pain harder to shake. That is why treatment looks at the postural, ergonomic and structural factors that keep loading the muscle, not only at the tender spot (Gerwin 2001).
Diagnosis and Assessment
No scan or blood test shows a trigger point. The diagnosis rests on examination by hand. Dr. Movshis takes a history of how the pain started and what makes it worse, then presses along the muscles for a taut band with a tender spot that reproduces your pain, and checks strength, flexibility and movement. Studies of whether two examiners find the same trigger points have given inconsistent results, and one review concluded the exam cannot yet be called reliable (Lucas 2009). The exam also has to rule out a pinched nerve, a joint problem or a disc, because referred muscle pain can mimic them. Imaging is ordered when the history or examination points to one of those, or to something more serious.
Treatment Options
Trigger point injections. Dr. Movshis places a fine needle into the trigger point, by feel or with ultrasound depending on the muscle, and injects a small amount of local anesthetic, 0.25% bupivacaine or 0.2% ropivacaine, sometimes with a small dose of steroid. Relief can be immediate, especially when the needle produces a brief twitch in the muscle (Hong 1994). The long-term evidence is more modest. A review of 23 trials found that the benefit did not depend on what was injected and may come largely from the needle itself (Cummings 2001), and a later review of 15 trials found no clear evidence either way in chronic pain, while noting that adding injections to stretching improved results (Scott 2009). So the injections are used to loosen a muscle enough to stretch and strengthen it, not on their own. Botox is not used for trigger points at Modal Pain Management NYC. The trigger point injections page covers the procedure and the evidence in detail.
Physical therapy and exercise. Stretching, strengthening and correcting the movement patterns that overload the muscle are the core of treatment, with a home program to keep the gains. Dry needling by a trained physical therapist is an alternative to injection for some people.
Medicines. A short course of a muscle relaxant or an anti-inflammatory can help during an acute spasm. Muscle relaxants often cause drowsiness, so they are used for a short time.
Nerve blocks. These are considered when a nerve problem is part of the pain rather than the muscle alone.
What to Expect
Most trigger point injection sessions take 15 to 30 minutes. You may feel a pinch, then pressure, and sometimes the brief twitch. Many patients notice relief right away. Soreness in the injected muscles for a day or two is common. In the classic trial it appeared within hours in 42% of patients injected with lidocaine (Hong 1994). There is no evidence-based number of sessions. Some people do well after one, others need a few, and some do not respond. If each session brings only brief relief, the plan should change rather than the injections being repeated. What to do afterward and the warning signs that need a call are on the trigger point injection aftercare page.
Prevention and Self-Care
Myofascial pain tends to come back when the load that caused it does. Set up your desk with the screen at eye level, a supportive chair and the keyboard where your wrists stay neutral. Get up and move regularly rather than holding one position for hours. Keep up strengthening and stretching, particularly for the neck, shoulders, back and core. Sleep and stress matter as well, because both make pain harder to shake. Heat and self-massage with a foam roller or a ball can ease tight muscles between visits. If the pain returns, an early visit is usually easier than undoing months of guarding.
References
- Fernández-de-Las-Peñas C, Dommerholt J. International Consensus on Diagnostic Criteria and Clinical Considerations of Myofascial Trigger Points: A Delphi Study. Pain Med. 2018;19(1):142–150. doi:10.1093/pm/pnx207 · PubMed
- Gerwin RD. Classification, epidemiology, and natural history of myofascial pain syndrome. Curr Pain Headache Rep. 2001;5(5):412–20. doi:10.1007/s11916-001-0052-8 · PubMed
- Shah JP, Thaker N, Heimur J, Aredo JV, Sikdar S, Gerber L. Myofascial Trigger Points Then and Now: A Historical and Scientific Perspective. PM R. 2015;7(7):746–761. doi:10.1016/j.pmrj.2015.01.024 · PubMed
- Scott NA, Guo B, Barton PM, Gerwin RD. Trigger point injections for chronic non-malignant musculoskeletal pain: a systematic review. Pain Med. 2009;10(1):54–69. doi:10.1111/j.1526-4637.2008.00526.x · PubMed
- Cummings TM, White AR. Needling therapies in the management of myofascial trigger point pain: a systematic review. Arch Phys Med Rehabil. 2001;82(7):986–92. doi:10.1053/apmr.2001.24023 · PubMed
- Hong CZ. Lidocaine injection versus dry needling to myofascial trigger point. The importance of the local twitch response. Am J Phys Med Rehabil. 1994;73(4):256–63. doi:10.1097/00002060-199407000-00006 · PubMed
- Lucas N, Macaskill P, Irwig L, Moran R, Bogduk N. Reliability of physical examination for diagnosis of myofascial trigger points: a systematic review of the literature. Clin J Pain. 2009;25(1):80–9. doi:10.1097/AJP.0b013e31817e13b6 · PubMed