Trigger point injections treat tight, tender knots in a muscle that reproduce your pain when pressed. At Modal Pain Management in Midtown Manhattan, Dr. Alex Movshis uses them for myofascial pain in the neck, shoulders, upper and lower back and buttock, as a way to release the muscle enough to stretch and strengthen it. Relief can be immediate, and the long-term evidence is more modest than many websites suggest, which is why the injections are paired with a stretching and exercise program rather than offered on their own.
What Are Trigger Points
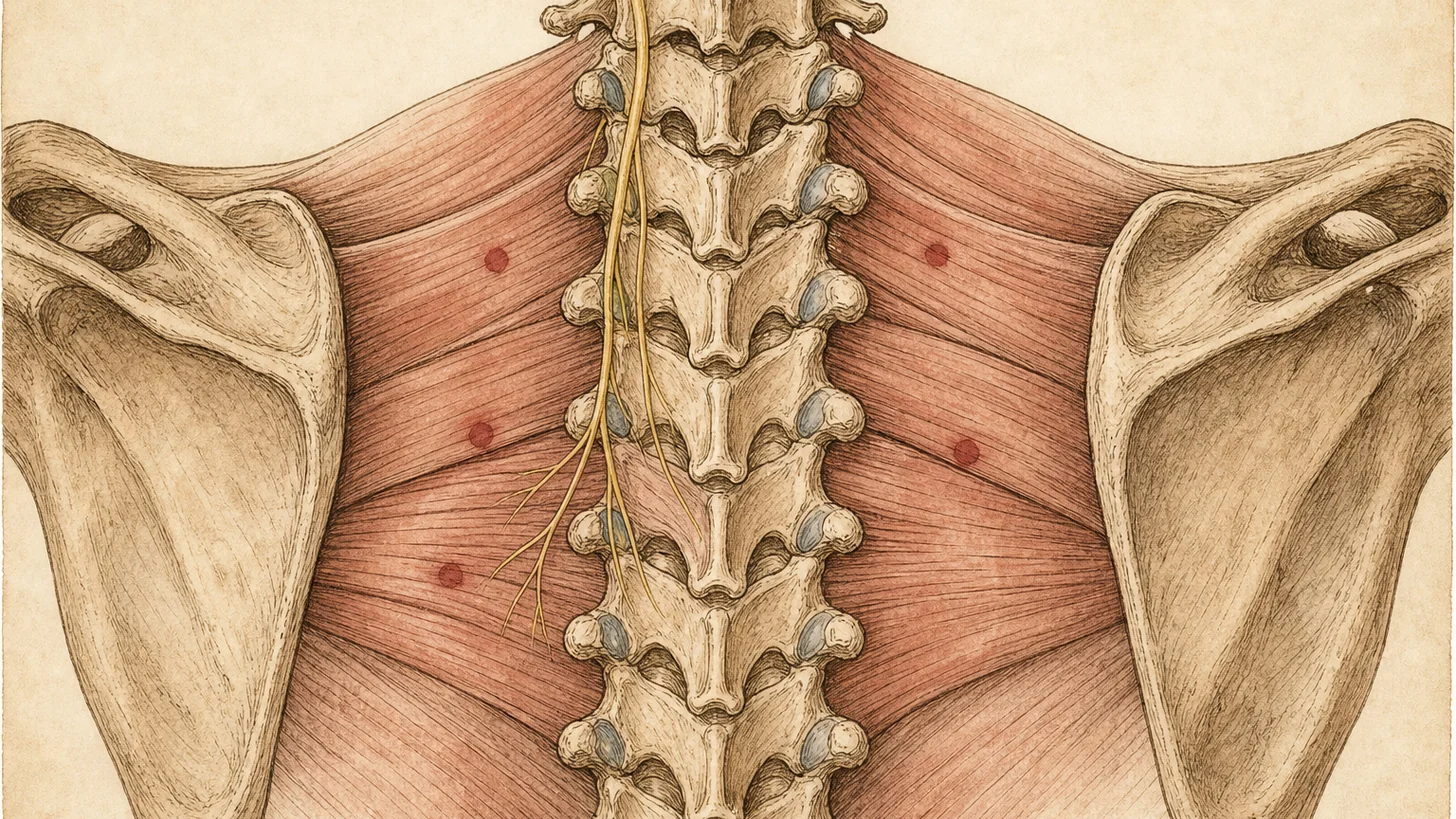
A myofascial trigger point is a sore spot inside a tight band of muscle. In 2018 an international panel of 60 experts agreed on three core features of a trigger point: a taut band you can feel, a hypersensitive spot within that band, and referred pain when it is pressed (Fernández-de-las-Peñas 2018). An active trigger point reproduces the pain you came in with, and you recognize it as your pain. A latent one is tender when pressed but doesn’t cause your everyday symptoms.
Why trigger points form is still debated. The classic explanation is that a small patch of muscle fibers gets stuck in a contracted state after overload or injury, and that idea has never been proven. Small studies that sampled the fluid around active trigger points found higher levels of chemicals linked to pain and inflammation than in normal muscle, and sensitization of the nervous system may play a part as well (Shah 2015). Some pain specialists go further and argue that trigger points are not a distinct physical lesion at all, while accepting that the pain and tenderness themselves are real (Quintner 2015).
Referred pain is the confusing part. In a study of 25 people with chronic tension-type headache and 25 without, pressing on active trigger points in the upper trapezius (the muscle running from the neck to the top of the shoulder), the sternocleidomastoid at the front of the neck or the temple muscle brought on the patients’ familiar headache. People without headaches had only latent trigger points in those muscles (Fernández-de-las-Peñas 2006). The 2018 expert panel also agreed that referred sensations can include tingling or burning, not only an ache, and that the area of referral doesn’t follow a fixed map (Fernández-de-las-Peñas 2018). That overlap with nerve pain is why the exam also has to rule out a pinched nerve or a joint problem. No scan or blood test shows a trigger point. Diagnosis rests on examination by hand, and studies of whether two examiners find the same points have given inconsistent results, especially for the taut band and the twitch, and one review concluded the exam can’t yet be called reliable (Lucas 2009).
Conditions Treated with Trigger Point Injections
The main use is myofascial pain syndrome, meaning regional muscle pain with active trigger points. It can be the main problem, or it can develop as a result of another condition. It is different from fibromyalgia, which is widespread pain. Long-standing myofascial pain can spread to more muscles, but one review holds that it does not turn into fibromyalgia (Gerwin 2001).
Neck pain and tension-type headache are common reasons to try them. In a randomized trial of 108 people with frequent episodic tension-type headache, a single session of lidocaine injections into trigger points in the head and neck muscles cut the number of headache days more than saline did at 2 and 4 months, but not at 6. A course of five sessions still beat five saline sessions at 6 months (Karadaş 2013). A special-interest section of the American Headache Society concluded that the injections seem to have a role as an add-on treatment for common headache disorders when active trigger points are found on exam (Robbins 2014).
Low back pain is a weaker case. A Cochrane review of injection therapy for subacute and chronic low back pain, which included injections into tender and trigger points, found insufficient evidence to support it, though it allowed that some subgroups may respond (Staal 2008). Injections make the most sense when the exam points clearly at a muscle rather than a disc, nerve or joint.
Shoulder pain is a similar story. In a study of 72 people with long-standing shoulder pain, one examiner found trigger points in every participant, most often in the infraspinatus on the back of the shoulder blade and in the upper trapezius (Bron 2011). That study counted trigger points and did not test injections. A torn or damaged rotator cuff tendon is a different problem and needs its own workup. Lingering neck muscle pain after whiplash is another use. Whiplash was among the conditions in the trials of one systematic review, whose overall verdict was still no clear evidence either way (Scott 2009). Athletes and other active people with a tender muscle that limits training are treated the same way, with the injection as one piece of a stretching and strengthening plan.
How the Procedure Works
The procedure starts with an examination. Dr. Movshis presses along the muscles to find a taut band with a tender spot that reproduces your pain. The skin over it is cleaned with antiseptic. He then advances a thin needle into the trigger point himself, by feel or with ultrasound guidance depending on the muscle and what lies beneath it. You may feel the muscle give a brief, involuntary twitch as the needle reaches the spot. The twitch is a useful sign that the needle is in the right place, though it doesn’t happen every time. A small amount of local anesthetic, 0.25% bupivacaine or 0.2% ropivacaine, sometimes with a small dose of steroid, is then injected into the trigger point. In a classic trial, relief right after the injection depended on producing that twitch response (Hong 1994). Several trigger points can be treated in one session. The injections typically take 15 to 30 minutes, depending on how many points are treated.
What to Expect
You will sit or lie in a position that gives access to the affected muscles. You may feel a slight pinch as the needle enters the skin, then pressure, and sometimes the brief twitch described above. Many patients notice relief right away. Soreness in the injected muscles for a day or two afterward is common. In the classic trial it appeared within hours in 42% of patients injected with lidocaine, against all of those treated with a dry needle (Hong 1994). What to do and not do afterward, how long the soreness lasts, and the warning signs that need a call or an emergency room are on the trigger point injection aftercare page.
What the Evidence Shows
Trigger point injections are widely used, and the research behind them is honest about its limits. A systematic review of 23 randomized trials found that, in the higher-quality trials, the effect did not depend on what was injected, and concluded that any benefit was likely due to the needle or placebo (Cummings 2001). A later review of 15 trials in chronic pain found no clear evidence of either benefit or ineffectiveness, and noted that adding injections to stretching improved results, as did ultrasound and laser (Scott 2009). For neck pain, a 2022 analysis of six trials found that injections reduced pain more than dry needling in the short term, with low certainty (Navarro-Santana 2022). Whether the drug matters is unsettled, and adding a steroid has not been shown to help: in a randomized trial in low back strain, the groups that received no drug did at least as well as lidocaine with or without triamcinolone (Garvey 1989).
What this means in practice: the injections are a tool to release a muscle enough to stretch and strengthen it. In a randomized trial of 102 patients, injections plus neck stretching and ultrasound plus neck stretching both did better than stretching alone after treatment, though by three months the stretching-only group had caught up and scored better, though the difference was not statistically significant (Esenyel 2000). Serious complications are rare, but they exist, including a collapsed lung after injections near the chest wall (Ahiskalioglu 2016), which is why we tell every patient what to watch for afterward.
Treatment Course
There is no evidence-based number of sessions. How many you need depends on how long the pain has been there, how many muscles are involved and how you respond to the first session. Some people do well after one session. Others need a few, spaced out, and some don’t respond. We recommend pairing the injections with physical therapy and a home stretching program, and with attention to posture and workstation setup, because myofascial pain needs attention to the postural, ergonomic and structural factors that affect the muscle, not just to the tender spot (Gerwin 2001). Insurers usually allow a repeat only when the previous session helped substantially and you are in a stretching or exercise program. The Medicare policy for New York, for example, requires at least 50% relief lasting at least six weeks, plus at least 50% better function, and allows no more than three sessions in any 12 months (CMS L39662). We don’t take Medicare, but its rules are a useful yardstick. Regular follow-up appointments allow us to monitor your progress, adjust your treatment plan as needed, and decide whether further injections are worthwhile. The aim is to need fewer injections over time, not more. If each session brings only brief relief, repeating it is unlikely to change that, and the plan should change instead.
References
- Fernández-de-Las-Peñas C, Dommerholt J. International Consensus on Diagnostic Criteria and Clinical Considerations of Myofascial Trigger Points: A Delphi Study. Pain Med. 2018;19(1):142–150. doi:10.1093/pm/pnx207 · PubMed
- Gerwin RD. Classification, epidemiology, and natural history of myofascial pain syndrome. Curr Pain Headache Rep. 2001;5(5):412–20. doi:10.1007/s11916-001-0052-8 · PubMed
- Shah JP, Thaker N, Heimur J, Aredo JV, Sikdar S, Gerber L. Myofascial Trigger Points Then and Now: A Historical and Scientific Perspective. PM R. 2015;7(7):746–761. doi:10.1016/j.pmrj.2015.01.024 · PubMed
- Scott NA, Guo B, Barton PM, Gerwin RD. Trigger point injections for chronic non-malignant musculoskeletal pain: a systematic review. Pain Med. 2009;10(1):54–69. doi:10.1111/j.1526-4637.2008.00526.x · PubMed
- Cummings TM, White AR. Needling therapies in the management of myofascial trigger point pain: a systematic review. Arch Phys Med Rehabil. 2001;82(7):986–92. doi:10.1053/apmr.2001.24023 · PubMed
- Navarro-Santana MJ, Sanchez-Infante J, Gómez-Chiguano GF, et al. Dry needling versus trigger point injection for neck pain symptoms associated with myofascial trigger points: a systematic review and meta-analysis. Pain Med. 2022;23(3):515–525. doi:10.1093/pm/pnab188 · PubMed
- Esenyel M, Caglar N, Aldemir T. Treatment of myofascial pain. Am J Phys Med Rehabil. 2000;79(1):48–52. doi:10.1097/00002060-200001000-00011 · PubMed
- Garvey TA, Marks MR, Wiesel SW. A prospective, randomized, double-blind evaluation of trigger-point injection therapy for low-back pain. Spine. 1989;14(9):962–4. doi:10.1097/00007632-198909000-00008 · PubMed
- Ahiskalioglu EO, Alici HA, Dostbil A, et al. Pneumothorax after trigger point injection: a case report and review of literature. J Back Musculoskelet Rehabil. 2016;29(4):895–897. doi:10.3233/BMR-160666 · PubMed
- Centers for Medicare & Medicaid Services. Local Coverage Determination L39662: Trigger Point Injections (TPI). Wellpoint Federal. CMS Medicare Coverage Database
- Hong CZ. Lidocaine injection versus dry needling to myofascial trigger point. The importance of the local twitch response. Am J Phys Med Rehabil. 1994;73(4):256–63. doi:10.1097/00002060-199407000-00006 · PubMed
- Fernández-de-Las-Peñas C, Alonso-Blanco C, Cuadrado ML, Gerwin RD, Pareja JA. Myofascial trigger points and their relationship to headache clinical parameters in chronic tension-type headache. Headache. 2006;46(8):1264–72. doi:10.1111/j.1526-4610.2006.00440.x · PubMed
- Quintner JL, Bove GM, Cohen ML. A critical evaluation of the trigger point phenomenon. Rheumatology (Oxford). 2015;54(3):392–9. doi:10.1093/rheumatology/keu471 · PubMed
- Lucas N, Macaskill P, Irwig L, Moran R, Bogduk N. Reliability of physical examination for diagnosis of myofascial trigger points: a systematic review of the literature. Clin J Pain. 2009;25(1):80–9. doi:10.1097/AJP.0b013e31817e13b6 · PubMed
- Karadaş Ö, Gül HL, Inan LE. Lidocaine injection of pericranial myofascial trigger points in the treatment of frequent episodic tension-type headache. J Headache Pain. 2013;14(1):44. doi:10.1186/1129-2377-14-44 · PubMed
- Robbins MS, Kuruvilla D, Blumenfeld A, et al. Trigger point injections for headache disorders: expert consensus methodology and narrative review. Headache. 2014;54(9):1441–59. doi:10.1111/head.12442 · PubMed
- Staal JB, de Bie R, de Vet HC, Hildebrandt J, Nelemans P. Injection therapy for subacute and chronic low-back pain. Cochrane Database Syst Rev. 2008;(3):CD001824. doi:10.1002/14651858.CD001824.pub3 · PubMed
- Bron C, Dommerholt J, Stegenga B, Wensing M, Oostendorp RA. High prevalence of shoulder girdle muscles with myofascial trigger points in patients with shoulder pain. BMC Musculoskelet Disord. 2011;12:139. doi:10.1186/1471-2474-12-139 · PubMed