A stiff neck after a bad night’s sleep usually settles on its own in a few days. Most acute neck pain improves with or without treatment, though close to half of people go on to have some ongoing pain or repeated flares (Cohen 2015). The point of this guide is to separate the neck pain that can be managed at home from the patterns that deserve a specialist’s exam, and the few that need emergency care.
Neck pain is common. In working adults, between about a quarter and a half report neck pain in a given year (Côté 2008). The causes range from simple muscle strain to problems in the discs, joints and nerves of the cervical spine.
Understanding the Complexity of Neck Pain
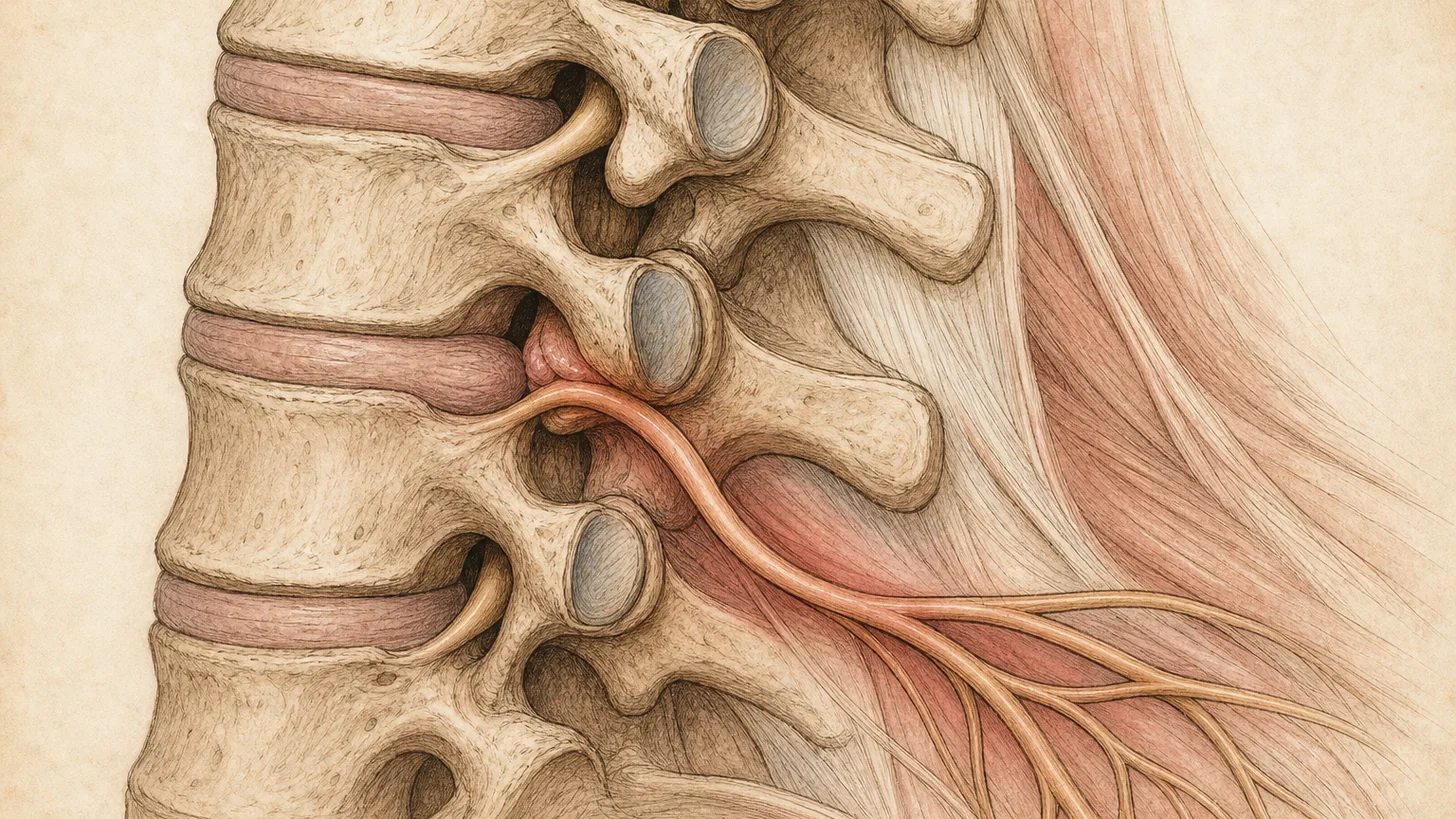
The cervical spine is seven vertebrae with the discs, joints, muscles, ligaments and nerve roots around them, holding up the head while letting it move in every direction. Several different structures can produce what feels like the same neck ache.
Common causes of neck pain include:
- Muscle strain from sustained postures or sudden movements
- Herniated or bulging cervical discs
- Cervical spinal stenosis
- Arthritis of the facet joints
- Whiplash injuries from motor vehicle accidents
- Pinched nerves (cervical radiculopathy)
- Headaches that start in the neck
Many neck problems settle with time and conservative care. The signs below are the ones that justify an exam.
7 Critical Warning Signs When to See a Neck Specialist
1. Persistent Pain Lasting More Than One Week
If your neck pain is not clearly improving after a week or two of sensible self-care, or has lasted more than a few weeks, it is worth having it examined. Pain that keeps going can come from a facet joint, a disc, a muscle trigger point or, less often, an inflammatory condition, and each has a different treatment.
Persistent pain may come from:
- Disc degeneration or herniation
- A facet joint
- Muscle trigger points
- Inflammatory conditions affecting the cervical spine
2. Radiating Pain, Numbness, or Tingling
When neck pain runs into the shoulder, arm or hand with numbness, tingling or weakness, a nerve root is likely involved. This is cervical radiculopathy, a nerve root irritated or compressed as it leaves the spine.
These symptoms deserve prompt evaluation because:
- Weakness in a specific muscle, or weakness that is getting worse, can mean significant nerve compression
- The level and cause can be identified, which guides treatment
- Most cases improve without surgery, and the exam helps decide whether yours needs anything more than time and therapy (Radhakrishnan 1994, Iyer 2016)
3. Severe Pain Following Trauma or Injury
Significant neck pain after a car accident, sports collision or fall needs emergency evaluation before anything else. Call 911 or go to the nearest emergency room, especially if there is numbness, weakness or severe pain. Whiplash can injure soft tissues and joints, and a fracture or ligament injury has to be ruled out.
Post-traumatic neck pain may come from:
- Ligament or muscle injury
- Fractures of cervical vertebrae
- Disc injuries
- Spinal cord injury
4. Morning Stiffness and Limited Range of Motion
Some morning stiffness is common. Severe stiffness that makes it hard to turn your head or look up, or stiffness that lasts a long time each morning, is worth evaluating.
This pattern can suggest:
- Cervical spondylosis (arthritis of the neck)
- Inflammatory conditions such as rheumatoid arthritis or ankylosing spondylitis
- Advanced disc degeneration
- Muscle spasm
5. Headaches Originating from the Neck
Cervicogenic headache starts in the upper cervical spine, most often the C2–C3 facet joint, and is felt at the base of the skull, often spreading forward on one side (Bogduk 2009). It overlaps with migraine and tension-type headache, and treatment is aimed at the neck. See our guide to cervicogenic headache.
Typical features:
- Pain starting at the back of the head
- One-sided head pain that stays on the same side
- Neck stiffness with the headache
- Pain brought on by neck movement or sustained postures
6. Muscle Spasms and Severe Stiffness
Muscle spasms that do not ease with heat, stretching and over-the-counter medication over a week or two deserve a look, because spasm is sometimes the muscles guarding an irritated joint or nerve.
When a tender knot in the muscle reproduces the pain and has not responded to stretching and therapy, trigger point injections can help it settle so the exercise program can work.
7. Sleep Disruption Due to Pain
Neck pain that regularly wakes you or keeps you from finding a comfortable position deserves an evaluation. Pain at night together with fever, weight loss or a history of cancer needs prompt medical attention.
Sleep disruption from neck pain can point to:
- A pinched nerve root
- A facet joint or disc problem that needs targeted treatment
- A pillow or sleep position that needs to change
- Rarely, infection or a tumor, especially with fever, weight loss or a cancer history
When Conservative Treatment Isn’t Enough
Trying conservative care first is reasonable for an ordinary neck strain. If you have tried the following for a week or two without clear improvement, it is time to be examined:
- Rest and activity modification
- Over-the-counter pain medications
- Ice and heat therapy
- Gentle stretching exercises
- Improved ergonomics at work
What to Expect During Your Consultation
A neck pain evaluation usually includes:
Detailed Medical History
Your doctor will ask about:
- Onset and duration of symptoms
- Previous injuries or trauma
- Work and lifestyle factors
- Previous treatments attempted
- Warning signs such as fever, weight loss, or trouble with hand coordination or walking
Physical Examination
The exam checks:
- Range of motion in all directions
- Muscle strength and reflexes
- Sensation in arms and hands
- Posture
- Tender points and muscle spasms
Diagnostic Testing
Many patients do not need imaging at the first visit. MRI shows abnormal findings in many people without pain, so it is used for nerve symptoms, red flags, pain that has not responded to treatment, or when a procedure is being planned (Cohen 2015). Depending on your symptoms, testing might include:
- X-rays to evaluate bone structure
- MRI to assess soft tissues, discs, and nerves
- CT scans for detailed bone imaging
- Nerve conduction studies if nerve damage is suspected
Treatment Options Available
Treatment depends on the cause. The main options are:
Non-Surgical Treatments
- Physical therapy and exercise, which the neck pain guideline recommends for most patients (Blanpied 2017)
- Cervical epidural steroid injections for a pinched nerve root
- Medial branch blocks to test a facet joint
- Trigger point injections for a muscle knot that reproduces the pain
- Radiofrequency ablation of the facet joint nerves, which can give months of relief in people who respond to medial branch blocks
Advanced Interventional Procedures
For chronic neck pain that has not responded to conservative treatment, image-guided procedures can be considered before surgery. The evidence varies by procedure. A 2015 review found weak positive evidence for radiofrequency denervation of the cervical facet joints and conflicting evidence for epidural steroid injections in radiculopathy (Cohen 2015).
The Importance of Early Intervention
Getting the right diagnosis early has practical advantages:
- The right treatment sooner: A pinched nerve, a facet joint and a muscle problem are treated differently, so identifying the source avoids months of the wrong treatment.
- Catching the rare serious cause: Spinal cord compression, infection and tumors are uncommon, and an exam is how they are picked up.
- A plan for recurrences: Many people have flares, and knowing the source makes each one easier to manage.
Choosing the Right Neck Specialist
When selecting a doctor for your neck pain, look for:
- Board certification in the relevant specialty
- Experience with image-guided procedures
- A careful exam of the neck, shoulder and arm, not just a review of the MRI
- Willingness to refer for surgery when it is the right answer
- A clear explanation of the options and the evidence behind them
Dual Board Certification Advantage
Dr. Movshis is board-certified in both anesthesiology and pain medicine. That training covers the diagnosis of spine and nerve pain and the image-guided procedures used to treat it.
When to Seek Emergency Care
Call 911 or go to the nearest emergency room for:
- Severe neck pain following significant trauma
- Sudden or rapidly worsening weakness in the arms or legs
- Loss of bladder or bowel control
- Severe headache with neck stiffness and fever
- Difficulty speaking or swallowing
Take Action for Your Neck Health
If you have any of the warning signs above, an exam can sort out which structure is involved and what will help. Many neck conditions can be treated without surgery, and when surgery is the right answer, that is part of the conversation too.
Modal Pain Management NYC is led by Dr. Alex Movshis, MD, dual board-certified in anesthesiology and pain medicine, who trained at the Icahn School of Medicine at Mount Sinai. For neck pain care in New York City, call (646) 290-6660 or visit modalpain.com/contact to schedule your consultation.
References
This article is reviewed against the peer-reviewed literature. Citations retrieved from PubMed.
- Cohen SP. Epidemiology, diagnosis, and treatment of neck pain. Mayo Clinic Proceedings. 2015. doi:10.1016/j.mayocp.2014.09.008 · PubMed
- Blanpied PR, Gross AR, Elliott JM, et al. Neck Pain: Revision 2017. The Journal of Orthopaedic and Sports Physical Therapy. 2017. doi:10.2519/jospt.2017.0302 · PubMed
- Côté P, van der Velde G, Cassidy JD, et al. The burden and determinants of neck pain in workers: results of the Bone and Joint Decade 2000-2010 Task Force on Neck Pain and Its Associated Disorders. Spine. 2008. doi:10.1097/BRS.0b013e3181643ee4 · PubMed
- Radhakrishnan K, Litchy WJ, O'Fallon WM, Kurland LT. Epidemiology of cervical radiculopathy. A population-based study from Rochester, Minnesota, 1976 through 1990. Brain. 1994. doi:10.1093/brain/117.2.325 · PubMed
- Iyer S, Kim HJ. Cervical radiculopathy. Current Reviews in Musculoskeletal Medicine. 2016. doi:10.1007/s12178-016-9349-4 · PubMed
- Bogduk N, Govind J. Cervicogenic headache: an assessment of the evidence on clinical diagnosis, invasive tests, and treatment. The Lancet Neurology. 2009. doi:10.1016/S1474-4422(09)70209-1 · PubMed
Frequently Asked Questions
If ordinary neck pain is not clearly improving after a week or two of rest, over-the-counter medication and gentle movement, or has lasted more than a few weeks, it is reasonable to be examined. Go sooner if the pain spreads into an arm, or comes with numbness, tingling or weakness, if it followed an injury, or if it wakes you at night. Most neck pain settles with time, and the exam is about finding the cases that need targeted treatment.
Pain that travels from the neck into the shoulder blade, arm or hand, especially in a strip toward particular fingers, points to a nerve root. Numbness or pins and needles in the same fingers, and weakness in specific movements such as bending the elbow, straightening it or gripping, add to the picture. Looking up and turning toward the painful side often makes it worse. Weakness that is getting worse needs prompt evaluation. Clumsy hands in both arms or unsteady walking suggest the spinal cord itself is involved and need urgent care.
Call 911 or go to the nearest emergency room for severe neck pain after a significant crash or fall, sudden or rapidly worsening weakness in the arms or legs, loss of bladder or bowel control, a severe headache with neck stiffness and fever, or difficulty speaking or swallowing. A sudden severe headache with neck pain, dizziness or double vision also needs emergency care, because it can be a tear in an artery in the neck. Neck or jaw pain with chest pressure, sweating or shortness of breath can be a heart attack.