Chronic pain is common, affecting more than 30% of people worldwide in some studies (Cohen 2021), and sorting through chronic pain treatment options in NYC can feel overwhelming. When pain persists for three months or longer, it affects sleep, work, mood and relationships, and those effects run in both directions. No single treatment fixes most chronic pain, but several have reasonable evidence when they are matched to the right source of pain.
Chronic pain differs from acute pain. Acute pain is a warning signal. Chronic pain is often better thought of as a condition in its own right, shaped by the original injury, changes in how the nervous system processes pain, and psychological and social factors (Cohen 2021).
Pain medicine now uses image-guided procedures that target a specific pain source, alongside exercise, psychological therapies and medication. For some people a procedure is the right next step. For others it is not, and a good pain physician will say so.
Understanding Chronic Pain: More Than Just Symptoms
Unlike acute pain that signals tissue damage and usually fades as healing occurs, chronic pain can persist beyond the normal healing time, and sometimes without ongoing tissue damage at all.
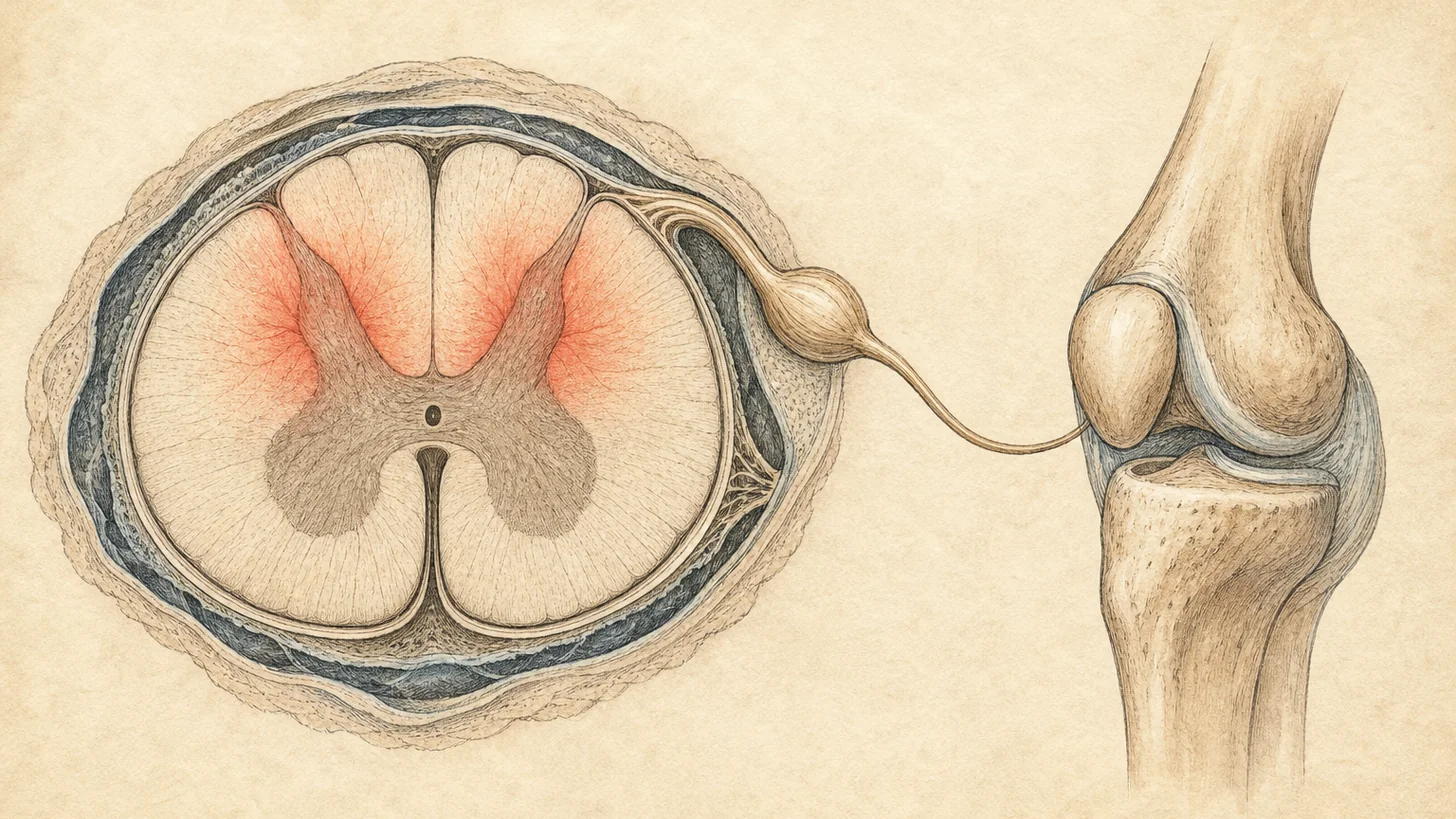
One reason is sensitization of pain pathways, where the nervous system becomes more responsive to input. This phenomenon, known as central sensitization, can make normally painless touch hurt and make ordinary pain last longer (Woolf 2011). It is thought to contribute in fibromyalgia, osteoarthritis, headache and post-surgical pain, among others, which is one reason simple pain medicines often fall short.
Common Chronic Pain Conditions
Several conditions frequently cause chronic pain in NYC patients:
- Low back pain: Often stemming from disc degeneration, facet joint arthritis, or spinal stenosis — frequently presenting as sharp pain when bending or sitting
- Neck pain: Commonly related to cervical disc issues or whiplash injuries
- Arthritis: Affecting joints throughout the body, particularly knees, hips, and spine
- Neuropathic pain: Resulting from nerve damage or dysfunction
- Myofascial pain syndrome: Involving trigger points in muscles and connective tissue
- Complex regional pain syndrome (CRPS): pain out of proportion to an injury, with changes in skin color, temperature or swelling in the limb
Each condition requires specific diagnostic approaches and tailored treatment strategies. What works for mechanical back pain may not be appropriate for neuropathic pain, highlighting the importance of accurate diagnosis and individualized treatment planning.
Evidence-Based Chronic Pain Treatment NYC: Beyond Medications
The opioid crisis pushed pain care toward non-opioid pain management. The 2022 CDC guideline asks clinicians to make the most of non-opioid treatments and to weigh the benefits and risks of opioids carefully (Dowell 2022).
Guidelines and trials generally favor a personalized combination of treatments, which might include medication, psychological therapy, exercise and procedures, over any single approach (Cohen 2021). The benefits of each piece are often modest. Cognitive behavioral therapy, the best-studied psychological treatment, gave small improvements in pain, disability and distress over usual care in a Cochrane review of 59 trials (Williams 2020). Physical therapy and exercise are part of nearly every plan.
Interventional Pain Management Techniques
Radiofrequency Ablation (RFA)
Radiofrequency ablation is one of the better-studied procedures for one specific kind of chronic pain, pain from the small facet joints of the spine. This minimally invasive procedure uses controlled heat to interrupt pain signals from the nerves that supply those joints.
It is used mainly for facet joint pain in the spine, after diagnostic nerve blocks have pointed to the joint (Cohen 2020). In people who respond, relief lasts about 9 months on average and sometimes more than a year (Smuck 2012). The procedure involves precise placement of specialized needles near the target nerves, followed by controlled heating that creates small lesions to interrupt pain transmission.
In carefully selected patients, about half to two-thirds report at least 50% less pain six months to two years after lumbar RFA (Conger 2020, Schneider 2020). Not every trial agrees. In a large Dutch trial, RFA added to an exercise program was no better than exercise alone (Juch 2017), and a 2025 BMJ guideline panel recommended against it for chronic back and neck pain (Busse 2025). The procedure is performed on an outpatient basis with minimal downtime, which suits a working NYC schedule.
Epidural steroid injections deliver anti-inflammatory medication next to irritated nerve roots, most often for leg pain from a herniated disc. Fluoroscopic guidance places the medication where it is meant to go. For radicular pain, pooled trials found the benefit small and short-lived (Chou 2015), and for leg pain lasting three months or longer a 2025 BMJ guideline panel recommended against epidural injections (Busse 2025). The injection works best for recent nerve-root pain, as a window for rehabilitation rather than a cure.
Joint Injections and Regenerative Medicine
For patients with osteoarthritis, tendon injuries, or joint degeneration, injection therapies deliver targeted treatment directly to damaged tissue. Corticosteroid injections can reduce pain within days, though the effect often fades over weeks to months, while platelet-rich plasma (PRP) is a slower, self-pay option whose evidence is mixed and varies by condition. Joint injections are performed under imaging guidance.
IV Therapy for Pain and Recovery
Some patients ask about physician-supervised IV therapy, including anti-inflammatory infusions and NAD+ IV therapy. Modal Pain Management NYC offers these, but the evidence that nutrient or NAD+ infusions relieve chronic pain is limited, so they are a supportive option at most and not a substitute for treating the source of the pain. Learn more about our full range of IV therapies.
Building Your Chronic Pain Treatment Plan
Effective chronic pain management rarely involves a single treatment. Most plans combine exercise or physical therapy, attention to sleep and mood, and, when the exam points to a specific source, a procedure. At Modal Pain Management NYC in Midtown Manhattan, Dr. Movshis creates personalized treatment plans that address your specific pain generators using evidence-based approaches — from nerve blocks and radiofrequency ablation to physical therapy.
If chronic pain is limiting your quality of life, book an appointment to discuss a treatment strategy designed specifically for your condition. Learn more about our full range of pain management services in NYC.
References
This article is reviewed against the peer-reviewed literature. Citations retrieved from PubMed.
- Cohen SP, Vase L, Hooten WM. Chronic pain: an update on burden, best practices, and new advances. The Lancet. 2021. doi:10.1016/S0140-6736(21)00393-7 · PubMed
- Woolf CJ. Central sensitization: implications for the diagnosis and treatment of pain. Pain. 2011. doi:10.1016/j.pain.2010.09.030 · PubMed
- Cohen SP, Bhaskar A, Bhatia A, et al. Consensus practice guidelines on interventions for lumbar facet joint pain from a multispecialty, international working group. Regional Anesthesia and Pain Medicine. 2020. doi:10.1136/rapm-2019-101243 · PubMed
- Chou R, Hashimoto R, Friedly J, et al. Epidural Corticosteroid Injections for Radiculopathy and Spinal Stenosis: A Systematic Review and Meta-analysis. Annals of Internal Medicine. 2015. doi:10.7326/M15-0934 · PubMed
- Williams ACC, Fisher E, Hearn L, Eccleston C. Psychological therapies for the management of chronic pain (excluding headache) in adults. The Cochrane Database of Systematic Reviews. 2020. doi:10.1002/14651858.CD007407.pub4 · PubMed
- Dowell D, Ragan KR, Jones CM, Baldwin GT, Chou R. CDC Clinical Practice Guideline for Prescribing Opioids for Pain - United States, 2022. MMWR Recommendations and Reports. 2022. doi:10.15585/mmwr.rr7103a1 · PubMed
- Smuck M, Crisostomo RA, Trivedi K, Agrawal D. Success of initial and repeated medial branch neurotomy for zygapophysial joint pain: a systematic review. PM&R. 2012. doi:10.1016/j.pmrj.2012.06.007 · PubMed
- Conger A, Burnham T, Salazar F, et al. The Effectiveness of Radiofrequency Ablation of Medial Branch Nerves for Chronic Lumbar Facet Joint Syndrome in Patients Selected by Guideline-Concordant Dual Comparative Medial Branch Blocks. Pain Medicine. 2020. doi:10.1093/pm/pnz248 · PubMed
- Schneider BJ, Doan L, Maes MK, et al. Systematic Review of the Effectiveness of Lumbar Medial Branch Thermal Radiofrequency Neurotomy, Stratified for Diagnostic Methods and Procedural Technique. Pain Medicine. 2020. doi:10.1093/pm/pnz349 · PubMed
- Juch JNS, Maas ET, Ostelo RWJG, et al. Effect of Radiofrequency Denervation on Pain Intensity Among Patients With Chronic Low Back Pain: The Mint Randomized Clinical Trials. JAMA. 2017. doi:10.1001/jama.2017.7918 · PubMed
- Busse JW, Genevay S, Agarwal A, et al. Commonly used interventional procedures for non-cancer chronic spine pain: a clinical practice guideline. BMJ. 2025. doi:10.1136/bmj-2024-079970 · PubMed