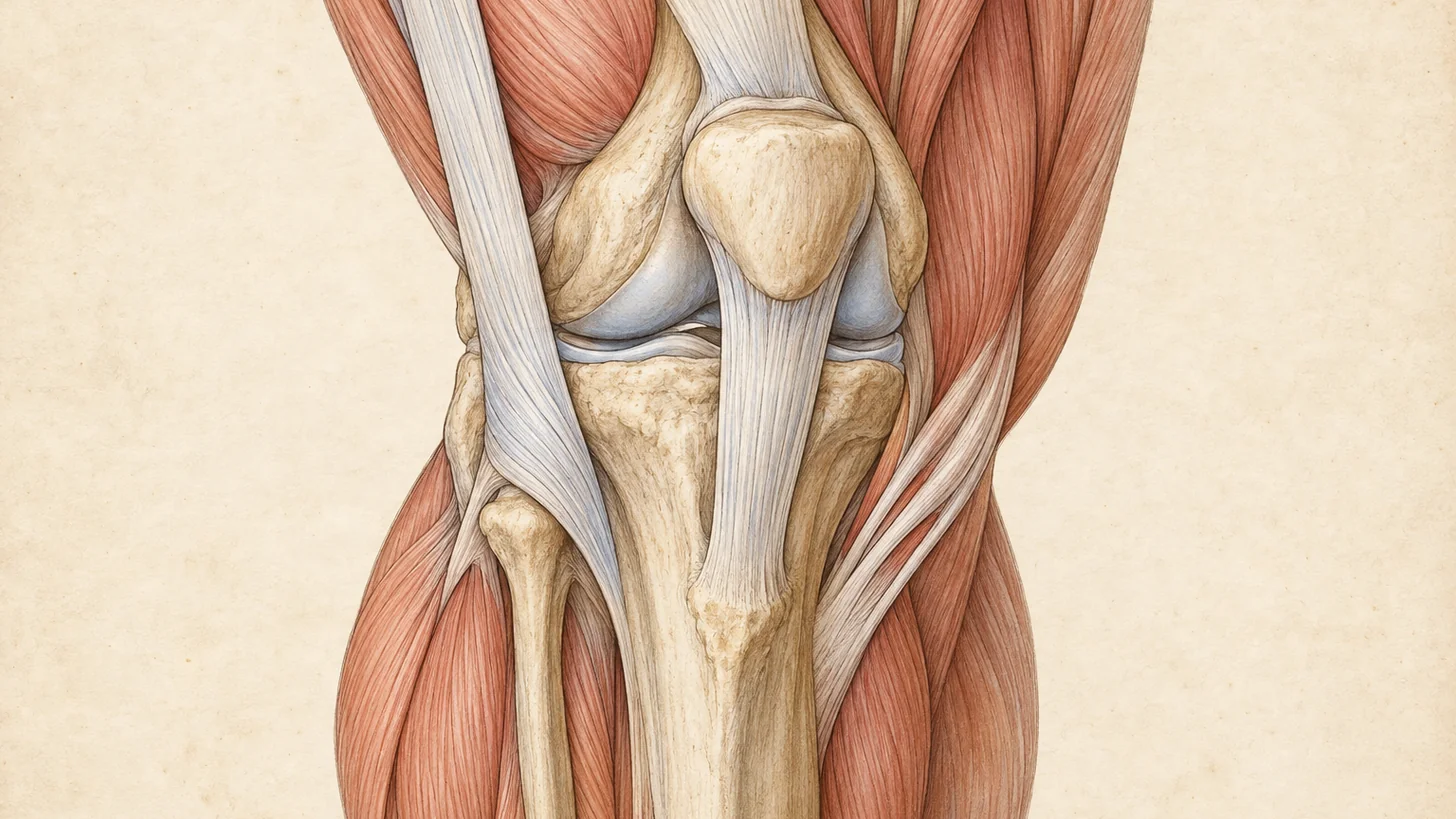
A common presentation in the middle of a marathon long-run block: a runner felt fine on the 18-miler, then winced walking down the subway stairs the next morning. No swelling, nothing popped, but it hurts on the way down and again after an hour at a desk. That runner rarely needs an MRI on day one. They need someone to put a finger on the right spot. Two questions do most of the sorting: where exactly does it hurt, and when in the run does it start?
| Where it hurts | When it shows up | Most likely diagnosis |
|---|---|---|
| Around or behind the kneecap | Stairs down, squats, after sitting, downhill running | Patellofemoral pain (runner’s knee) |
| One spot just below the kneecap | First mile, eases when warm, back after the run and next morning | Patellar tendinopathy |
| Outside of the knee | At a predictable mile, worse downhill, gone when walking | IT band syndrome |
| Inner shin, just below the joint line | Stairs, rising from a chair | Pes anserine bursitis or tendinopathy |
| Inner joint line, with swelling or catching | Twisting, deep squats, swelling after runs | Medial meniscus tear |
| Deep joint-line ache, runner over 50 | Morning stiffness, swelling after long runs | Knee osteoarthritis |
Around or behind the kneecap: patellofemoral pain (runner’s knee)
Runner’s knee is a diffuse ache. Ask the patient to point to it and they use the whole palm, not a fingertip. It gets worse whenever the quadriceps has to control a bent knee under load: going down stairs, squatting, running downhill, and sitting through a movie or a long meeting with the knees bent (van der Heijden 2015). There is little or no swelling, and the knee does not lock. In runners it usually follows a jump in volume or hill work.
The 2016 international patellofemoral pain consensus named exercise therapy the treatment of choice and recommended combining hip and knee strengthening in preference to knee exercises alone (Crossley 2016). The Cochrane review behind that recommendation pooled 31 trials with 1,690 participants. Exercise reduced pain during activity and improved function compared with no exercise, and hip-plus-knee programs beat knee-only programs for pain, though the authors rated the evidence very low quality because most trials were small and unblinded (van der Heijden 2015).
In a randomized trial of 69 runners with patellofemoral pain, education on symptom management and training modification alone produced the same improvement over 20 weeks as education plus an exercise program or education plus gait retraining (Esculier 2018). Cut volume and hills to what the knee tolerates, then build back gradually.
Cadence is the one form change worth trying. In 45 healthy recreational runners, raising step rate 5 to 10 percent above their preferred rate at the same speed reduced the energy absorbed at the knee on each landing (Heiderscheit 2011). That was a biomechanics study in uninjured runners, not a treatment trial, so treat it as a low-risk adjustment rather than a cure.
Injections are rarely the answer here. There is usually no single inflamed structure to target, and cortisone into the joint does not build the capacity the knee is missing. Don’t expect it to vanish on its own either. In a 5 to 8 year follow-up of patients diagnosed with patellofemoral pain, 34 of the 60 who responded reported an unfavorable recovery, and symptoms lasting more than 12 months at diagnosis predicted a worse course (Lankhorst 2016).
If the pain sits around the kneecap and is worse on stairs and after sitting, then start with a supervised hip-and-knee program through physical therapy for runner’s knee, after an exam confirms nothing structural is behind it.
One spot just below the kneecap, worst at the start of the run: patellar tendinopathy
Patellar tendinopathy, or jumper’s knee, hurts at the lower tip of the kneecap where the tendon attaches. You can find it with a fingertip. The running pattern is pain in the first mile that eases once warm, returns after the run, and is worse the next morning. Because the tendon and the infrapatellar bursa sit on top of each other, a few minutes of bedside ultrasound separates the two.
Tendons respond to load, so the treatment is load. A randomized trial in 76 patients, mostly athletes, with ultrasound-confirmed patellar tendinopathy compared a staged progressive tendon-loading program with the older eccentric decline-squat protocol. At 24 weeks the progressive program improved the VISA-P score by 28 points versus 18 for eccentrics (Breda 2021).
What not to do is put cortisone into the patellar tendon. Across randomized trials of tendinopathy, with the clearest data from the elbow, steroid injections relieved pain in the short term, but the effect reversed at intermediate and long-term follow-up (Coombes 2010). A clinical review of patellar tendinopathy specifically notes that corticosteroid injection increases the risk of tendon rupture (Schwartz 2015). For a tendon loaded on every stride, we don’t make that trade.
PRP is the honest middle ground. In the most cited double-blind trial, 23 patients received ultrasound-guided dry needling with or without leukocyte-rich PRP, alongside eccentric exercise. The PRP group was ahead at 12 weeks, but by 26 weeks the groups were no different (Dragoo 2014). A broader review concluded the PRP evidence in patellar tendinopathy is mixed and does not support firm recommendations (Schwartz 2015). It is an option for a tendon that has failed a real loading program.
If the pain is a fingertip spot below the kneecap that warms up and comes back, then a loading program comes first, with ultrasound-guided PRP for patellar tendinopathy reserved for the tendon that hasn’t responded. The evaluation runs through the sports medicine service.
Outside of the knee, at a predictable mile: IT band syndrome
IT band syndrome keeps a schedule. Runners tell you it starts at mile four, sharp on the outside of the knee just above the joint line, and builds until they have to stop. Walking is fine. Downhill running, slower paces, and the camber of a road shoulder tend to make it worse.
It is the most common cause of outside-knee pain in runners, with incidence estimates between 5 and 14 percent, but the treatment literature is thin and conflicting (van der Worp 2012). The same review pointed to hip and knee coordination, running style, and hip strengthening as the factors that seem to matter.
If the pain is on the outside of the knee and arrives at a predictable point in the run, then go to the full IT band syndrome evaluation and treatment page, which covers the rehab sequence and when an injection is reasonable.
Inside of the knee: pes anserine bursitis or a medial meniscus tear
Inner-knee pain splits on one question: below the joint line or on it?
Below the joint line, on the inner shin. The pes anserine is where three tendons (sartorius, gracilis, semitendinosus) attach a couple of inches below the inner joint line, with a bursa underneath them. Pain there is tender to a fingertip, worse on stairs and getting up from a chair, and often shows up in runners whose knees drift inward on landing. Treatment is hip and quadriceps strengthening plus load changes. When ultrasound confirms a fluid-filled bursa that hasn’t settled, an ultrasound-guided cortisone injection into the bursa, not the tendons, is reasonable. The knee bursitis page, which covers pes anserine bursitis, has the full ladder.
On the joint line, with swelling, catching, or locking. Pain right on the inner joint line, swelling after runs, a catching sensation, or pain with twisting and deep squats points to the medial meniscus. With mechanical symptoms, that knee gets an MRI and an orthopedic surgery opinion. A torn fragment that blocks motion is a mechanical problem, and no injection fixes it.
Over 50, stiff in the morning, aching along the joint line: knee osteoarthritis
Runners over 50 sometimes describe a knee that is stiff for the first several minutes out of bed, aches deep along the joint line rather than at one spot, and puffs up after long runs. That is knee osteoarthritis, and the next question is whether running caused it.
For recreational runners the best available data says no. A meta-analysis that pooled 17 studies and more than 114,000 people found hip and knee osteoarthritis in 3.5 percent of recreational runners, 10.2 percent of sedentary controls, and 13.3 percent of competitive runners (Alentorn-Geli 2017). The authors could not prove causation in either direction, and earlier knee injury is a likely confounder. Nothing in that data supports quitting recreational running to protect your knees.
Osteoarthritis in a runner is managed to keep them running, with strength work, volume and surface changes, and image-guided injection or genicular nerve radiofrequency ablation for a knee that starts limiting walking. The knee osteoarthritis page covers the evidence for each option, and the older-adult guide to non-surgical treatment for an arthritic knee in NYC walks through the decision for people who no longer run.
When knee pain after running is not an overuse problem
These can’t wait for a routine appointment:
- Bone pain that builds through the run and lingers at rest or at night, with tenderness you can pin to one spot on the shin bone or just below the knee. That is a possible stress fracture. Stop running and get imaged before the next run.
- A knee that swells quickly after a twist, gives way, or locks so it won’t fully straighten. That needs a physician exam within a day or two, not a rehab trial.
- Inability to bear weight after a fall or a misstep on the run.
- A hot, red, swollen knee with fever or chills. That can be a joint infection. Call 911 or go to the nearest emergency room.
Racing with a sore knee when your goal race is close
With a marathon or half marathon a few weeks out, the question is whether to race at all.
Reasonable to keep training and race: pain that is mild, doesn’t change your stride, settles within a day, and is stable or improving week to week. Taper as planned, cut the volume that provokes the knee, and don’t make up missed miles. In a cohort of 874 novice runners, those who increased weekly distance by more than 30 percent had a higher rate of distance-related injuries, including patellofemoral pain, IT band syndrome, and patellar tendinopathy, than those who increased by less than 10 percent. The finding was exploratory and its confidence interval crossed no effect (Nielsen 2014), but cramming missed miles into the final weeks is exactly that spike.
Not reasonable: pain that builds through every run, makes you limp, or is worse each morning than the day before. Any red flag above, focal bone tenderness most of all.
A cortisone shot to get through the race: never use one to mask pain from a structure you are about to load for the full race distance. If the pain comes from a tendon or might be bone stress, an injection turns off the warning while the tissue keeps taking damage. A bursitis confirmed on ultrasound, treated with enough lead time to see the response, is a different conversation that starts with an exam.
Weeks out, an evaluation leaves time to change the plan. In race week it mostly leaves time to say no. If cutting volume hasn’t changed the pain, or you can’t tell which pattern is yours, the exam is the shortcut, and you can verify your insurance before the visit.
References
- Crossley KM, van Middelkoop M, Callaghan MJ, Collins NJ, Rathleff MS, Barton CJ. 2016 Patellofemoral pain consensus statement from the 4th International Patellofemoral Pain Research Retreat, Manchester. Part 2: recommended physical interventions (exercise, taping, bracing, foot orthoses and combined interventions). Br J Sports Med. 2016;50(14):844–52. doi:10.1136/bjsports-2016-096268 · PubMed
- van der Heijden RA, Lankhorst NE, van Linschoten R, Bierma-Zeinstra SM, van Middelkoop M. Exercise for treating patellofemoral pain syndrome. Cochrane Database Syst Rev. 2015;1:CD010387. doi:10.1002/14651858.CD010387.pub2 · PubMed
- Esculier JF, Bouyer LJ, Dubois B, et al. Is combining gait retraining or an exercise programme with education better than education alone in treating runners with patellofemoral pain? A randomised clinical trial. Br J Sports Med. 2018;52(10):659–666. doi:10.1136/bjsports-2016-096988 · PubMed
- Heiderscheit BC, Chumanov ES, Michalski MP, Wille CM, Ryan MB. Effects of step rate manipulation on joint mechanics during running. Med Sci Sports Exerc. 2011;43(2):296–302. doi:10.1249/MSS.0b013e3181ebedf4 · PubMed
- Lankhorst NE, van Middelkoop M, Crossley KM, et al. Factors that predict a poor outcome 5-8 years after the diagnosis of patellofemoral pain: a multicentre observational analysis. Br J Sports Med. 2016;50(14):881–6. doi:10.1136/bjsports-2015-094664 · PubMed
- Breda SJ, Oei EHG, Zwerver J, et al. Effectiveness of progressive tendon-loading exercise therapy in patients with patellar tendinopathy: a randomised clinical trial. Br J Sports Med. 2021;55(9):501–509. doi:10.1136/bjsports-2020-103403 · PubMed
- Coombes BK, Bisset L, Vicenzino B. Efficacy and safety of corticosteroid injections and other injections for management of tendinopathy: a systematic review of randomised controlled trials. Lancet. 2010;376(9754):1751–67. doi:10.1016/S0140-6736(10)61160-9 · PubMed
- Schwartz A, Watson JN, Hutchinson MR. Patellar Tendinopathy. Sports Health. 2015;7(5):415–20. doi:10.1177/1941738114568775 · PubMed
- Dragoo JL, Wasterlain AS, Braun HJ, Nead KT. Platelet-rich plasma as a treatment for patellar tendinopathy: a double-blind, randomized controlled trial. Am J Sports Med. 2014;42(3):610–8. doi:10.1177/0363546513518416 · PubMed
- van der Worp MP, van der Horst N, de Wijer A, Backx FJ, Nijhuis-van der Sanden MW. Iliotibial band syndrome in runners: a systematic review. Sports Med. 2012;42(11):969–92. doi:10.2165/11635400-000000000-00000 · PubMed
- Alentorn-Geli E, Samuelsson K, Musahl V, Green CL, Bhandari M, Karlsson J. The Association of Recreational and Competitive Running With Hip and Knee Osteoarthritis: A Systematic Review and Meta-analysis. J Orthop Sports Phys Ther. 2017;47(6):373–390. doi:10.2519/jospt.2017.7137 · PubMed
- Nielsen RØ, Parner ET, Nohr EA, Sørensen H, Lind M, Rasmussen S. Excessive progression in weekly running distance and risk of running-related injuries: an association which varies according to type of injury. J Orthop Sports Phys Ther. 2014;44(10):739–47. doi:10.2519/jospt.2014.5164 · PubMed
Frequently Asked Questions
Start by working out where it hurts, because the fix depends on the structure. For a diffuse ache around the kneecap (runner's knee) or one tender spot just below it (patellar tendinopathy), cut the mileage and hills that provoke it back to a level the knee tolerates, start a progressive hip and knee strengthening program, and try raising your cadence about 5 percent. In a biomechanics study of recreational runners, a 5 to 10 percent higher step rate at the same speed lowered the energy absorbed at the knee on each landing (Heiderscheit 2011). Sharp outside-knee pain that arrives at the same mile every run is IT band syndrome, which has its own rehab. Avoid sudden jumps in weekly distance. Pain that builds through every run, makes you limp, or is worse each morning needs an exam rather than more stretching.
Runner's knee (patellofemoral pain) is fixed with load, not with an injection. The 2016 international consensus recommends exercise therapy as the treatment of choice, and specifically recommends combining hip and knee strengthening over knee exercises alone (Crossley 2016). Training education matters as much as the exercise sheet: in a randomized trial of 69 runners, education on symptom management and training modification alone improved symptoms as much as education plus exercises or gait retraining (Esculier 2018). In practice that means reducing volume and downhill running to a tolerable level, strengthening the hips and quadriceps for several months, and rebuilding mileage gradually. A supervised <a href="/treatments/physical-therapy/">physical therapy program</a> keeps the progression honest.
For most runners it settles with a structured program, but it is not reliably self-limiting. In a long-term follow-up of patients diagnosed with patellofemoral pain, 57 percent of those who responded reported an unfavorable recovery 5 to 8 years later, and pain that had lasted more than 12 months at diagnosis predicted a worse course (Lankhorst 2016). Only a fifth of the original patients answered, so the true figure is uncertain, but the direction is clear: waiting it out is a weak strategy. The Cochrane review found consistent, though very low quality, evidence that exercise therapy improves long-term recovery (van der Heijden 2015). Start the rehab early rather than after a year of on-and-off running.
A diffuse ache around or behind the kneecap that you point to with your whole palm rather than one fingertip. It flares when the quadriceps controls a bent knee under load: walking down stairs, squatting, running downhill, and sitting through a long meeting or a movie with the knees bent (van der Heijden 2015). Swelling is usually minimal and the knee does not lock or give way. Pain at one precise spot on the tendon below the kneecap points to patellar tendinopathy instead, and pain on the outside of the knee at a set mile points to IT band syndrome. Swelling, locking, or giving way suggest a structural problem that needs an exam.
The usual answer is iliotibial band syndrome, the most common cause of outside-knee pain in runners, with incidence estimates between 5 and 14 percent (van der Worp 2012). The pattern is distinctive: sharp pain just above the joint line on the outside of the knee that starts at a predictable point in the run, builds until you stop, and is fine when walking. Downhill running and slower paces tend to make it worse. Treatment centers on hip strengthening, running form, and adjusting the training that provokes it. See the <a href="/services/it-band-syndrome/">IT band syndrome page</a> for the full rehab sequence and when an injection is reasonable.
It depends on how the pain behaves, not how much it hurts on one day. Running is usually reasonable when the pain is mild, does not change your stride, settles within a day, and is stable or improving week to week. Stop and get examined when pain builds through each run, makes you limp, is worse the next morning than the day before, or sits on one spot of bone. Bone pain that lingers at rest can be a stress fracture. A knee that locks, gives way, or swells quickly after a twist needs a prompt exam. A hot, swollen knee with fever needs you to call 911 or go to the nearest emergency room.
Rarely, and never into the patellar tendon. Runner's knee usually has no single inflamed structure to inject, and cortisone does not build the strength the knee is missing. For tendinopathy, randomized trials show steroid injections relieve pain in the short term but the benefit reverses at intermediate and long-term follow-up (Coombes 2010), and a review of patellar tendinopathy specifically notes increased rupture risk (Schwartz 2015). Cortisone does have a role for a confirmed, fluid-filled bursitis such as pes anserine bursitis, given under ultrasound guidance. Using a shot to mask pain so you can race through a tendon or bone injury is a bad trade.